Prenatal NICU consult coding uses 99221-99223. Without consult codes, bill it on the mother’s claim as an initial hospital visit. The fix: pick the level by total time or MDM, and do not bill visits that meet neither.
Counseling time counts toward the code. A short talk with no time noted and no real decision making is hard to defend as 99221.
TL;DR: The pregnant inpatient is the patient, so bill her claim, not the unborn baby’s. A first visit by the neonatology team is an initial hospital service, 99221-99223, even if obstetrics already saw her. 99221 needs straightforward or low MDM or at least 40 minutes of total time on the date. Use O60.0- preterm labor without delivery plus a Z3A weeks code. If the visit meets neither MDM nor time, it is not billable as 99221.
Written by Manikandan J, CPC, CRCR, a certified coder and revenue cycle specialist. Published 18 November 2026. Last updated: 18 November 2026.
Table of Contents
What code do you use for a prenatal NICU consult when you do not bill consult codes?
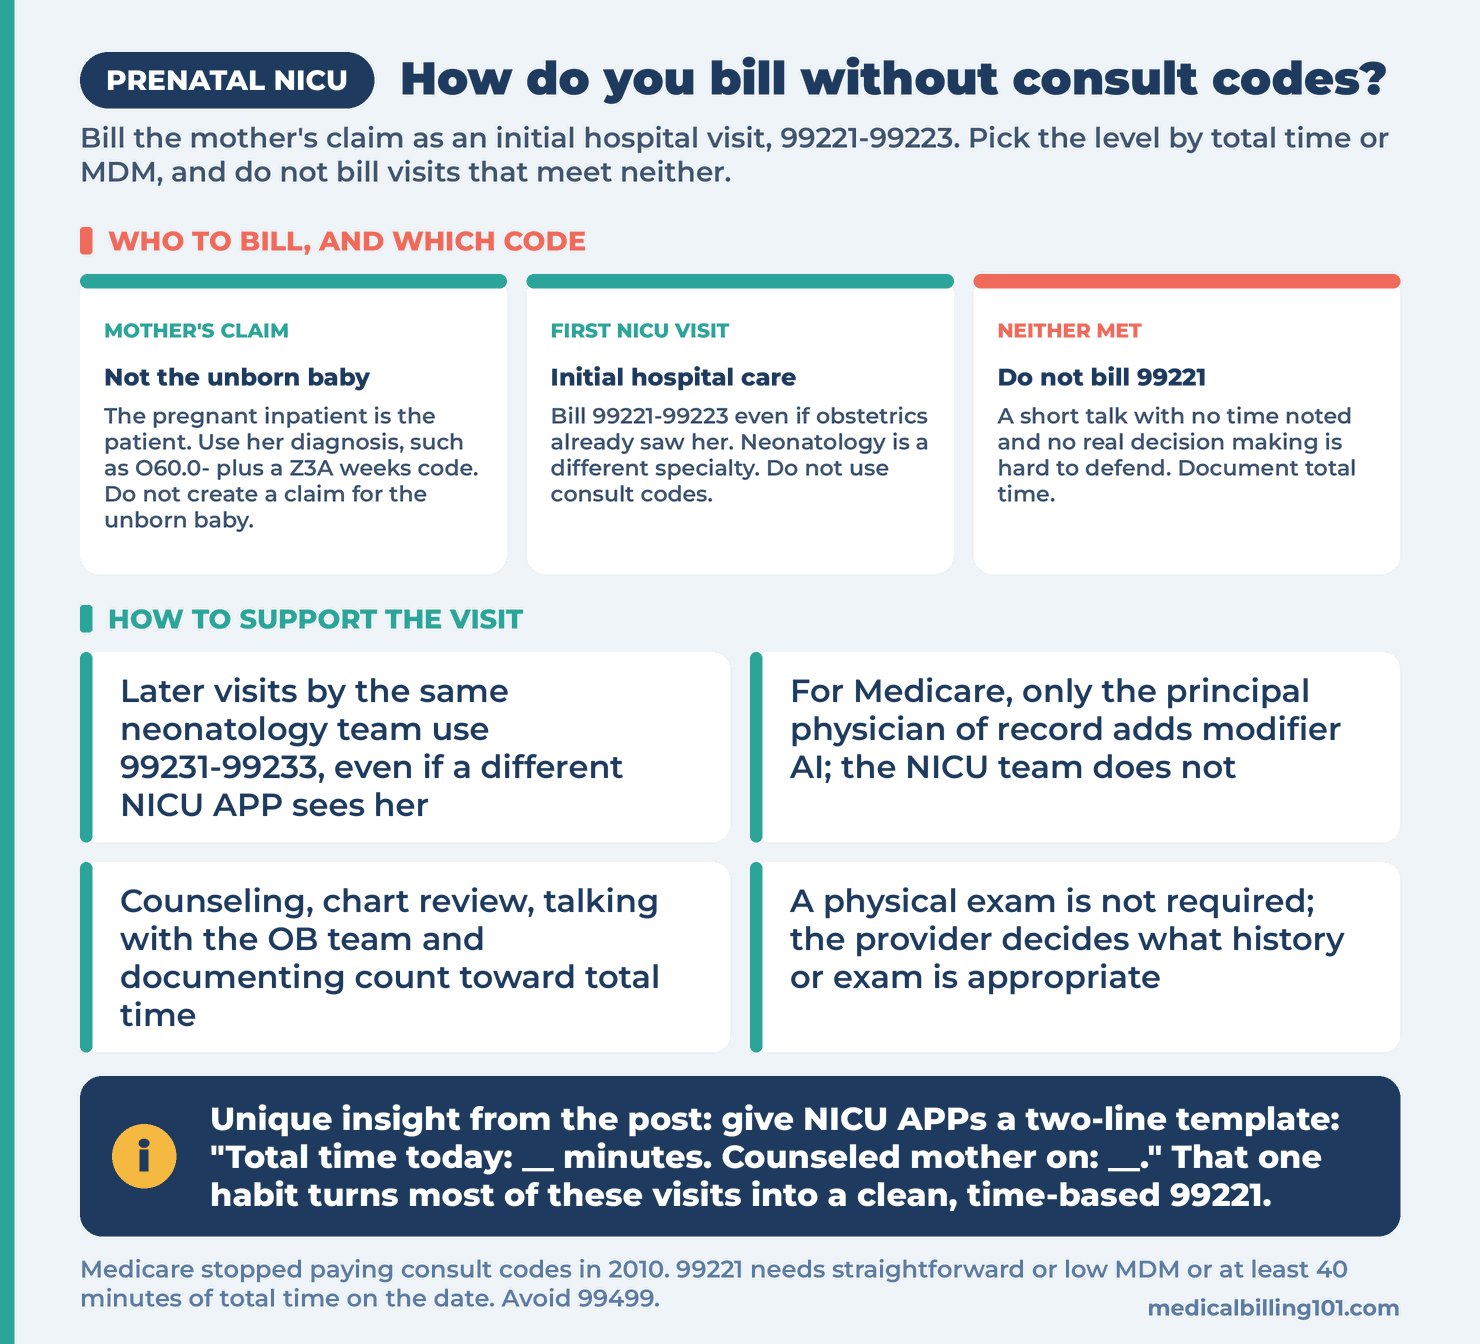
Initial hospital inpatient or observation care is the CPT code family 99221-99223 for the first visit in a stay. Use it for the NICU team’s first prenatal visit to the mother. Medicare stopped paying consult codes in 2010. Per the Medicare Claims Processing Manual, Chapter 12, section 30.6.10, practitioners bill the initial hospital care code that fits the work.
Many groups follow the same rule for all payers to keep coding simple. That is a valid choice. It means the visit has to meet the 99221-99223 descriptors, not the lower bar of the old consult codes.
The same manual says a practitioner must meet all 99221 requirements to report it. CMS notes those requirements are higher than the old 99251 and 99252 consult codes.
Is it an initial or subsequent visit if OB already admitted the mother?
It is initial for the NICU team. The AMA E/M guidelines call a service initial when the patient has had no professional services from the same group, same exact specialty and subspecialty, during the stay. OB and maternal-fetal medicine are a different specialty from neonatology.
APPs follow the specialty of the physicians they work with. The AMA guidelines say nurse practitioners and physician assistants count as the same specialty as their physicians. So a NICU nurse practitioner counts as neonatology, not as OB.
- First neonatology visit this stay. Bill 99221, 99222 or 99223.
- Second neonatology visit, same stay. Bill 99231, 99232 or 99233, even if a different NICU APP sees her.
- Admitting physician only. For Medicare, only the principal physician of record adds modifier AI. The NICU team does not.
Our answer on 99221 for observation or inpatient patients covers the same specialty test for other consulting teams.
Does a counseling-only visit support 99221?
It can, when total time reaches 40 minutes. 99221 needs a medically appropriate history and/or exam, plus straightforward or low MDM. Or it needs at least 40 minutes of total time on the date. A physical exam is not required. The provider decides what history or exam is appropriate.
Total time is all the time the provider spends on the patient on the date of the visit. Time is usually the cleaner path for these visits. The AMA guidelines list counseling and educating the patient and family as countable time. Chart review, talking with the OB team and documenting also count. Travel and general teaching do not count.
| Code | MDM level | Total time on the date |
|---|---|---|
| 99221 | Straightforward or low | 40 minutes or more. |
| 99222 | Moderate | 55 minutes or more. |
| 99223 | High | 75 minutes or more. |
| 99231 (later visit) | Straightforward or low | 25 minutes or more. |
The old rule that counseling must be over half the visit is gone. The total time just has to meet the minimum. Our E/M coding cheat sheet lists every time minimum on one screen.
Can MDM carry the level when there is no exam?
Sometimes, but it is the weaker path here. Medical decision making (MDM) is the E/M element that scores the problems addressed, the data reviewed and the risk of management. A counseling talk often addresses a serious problem but involves few orders or decisions by the NICU APP.
Coders can score the note with our E/M level calculator. If MDM lands below straightforward, use time or do not bill. Our MDM answer on a cancer patient visit shows how auditors read the problem and risk columns.
Which diagnosis codes go on the mother’s claim?
ICD-10-CM is the U.S. diagnosis code set. Use the mother’s condition, since she is the patient. The CDC ICD-10-CM browser lists O60.02 for preterm labor without delivery, second trimester, and O60.03 for the third trimester. Add a Z3A code for the weeks of gestation, such as Z3A.30 for 30 weeks.
Do not create a claim for the unborn baby. The baby has no account or coverage yet. If the baby is born and the NICU team later treats the baby, those services go on the baby’s own claim.
What if the visit meets neither time nor MDM?
Then do not bill it as 99221. A brief talk with no time noted and no real MDM does not meet the descriptor. Treat it as a non-billable service, or fix the documentation habit for the next visit.
One Medicare point is worth knowing. Chapter 12, section 30.6.10, says a subsequent hospital care code could fit work that the old low-level consult codes described. CMS tells contractors not to find fault when the record supports that subsequent code. Many of these mothers have Medicaid or commercial plans, so check each payer before using it.
Avoid 99499, the unlisted E/M code. The same chapter limits it to rare cases with no other fitting code, and it needs manual review.
In my AR work, the inpatient E/M lines that failed audits most often had no total time in the note.
Give NICU APPs a two-line template: “Total time today: __ minutes. Counseled mother on: __.” That one habit turns most of these visits into a clean, time-based 99221. If you get a payer review later, our guide to handling a Medicare MAC prepayment review walks through the record request.
3-step checklist
- Bill the mother’s claim with O60.0- and a Z3A code, never the unborn baby’s.
- Use 99221-99223 for the first neonatology visit and 99231-99233 after that.
- Document total time; skip billing if neither time nor MDM meets 99221.
FAQ
What code do you use for a prenatal NICU consult without consult codes?
Use the initial hospital care codes 99221-99223 for the NICU team’s first visit to the mother during the stay. Later visits by the same team use 99231-99233.
Can a NICU APP bill 99221 if OB already saw the mother?
Yes. Neonatology is a different specialty from OB and maternal-fetal medicine, so the NICU team’s first visit is an initial service. APPs count as the specialty of the physicians they work with.
Does a prenatal counseling visit need a physical exam for 99221?
No. 99221 needs a medically appropriate history and/or exam, plus straightforward or low MDM or at least 40 minutes of total time on the date.
Does counseling time count toward 99221?
Yes. Counseling and educating the patient and family count toward total time, along with chart review, care coordination and documenting on the same date.
Whose claim gets the prenatal NICU counseling visit?
The mother’s claim. She is the patient, so use her diagnosis, such as O60.02 or O60.03 with a Z3A weeks code. The unborn baby is not billed.
Sources
My methodology was simple. I checked the AMA E/M guidelines, the Medicare Claims Processing Manual and the CDC ICD-10-CM browser. Medicaid and commercial payers may apply their own consult and visit rules, so check each payer’s policy.
- AMA, CPT E/M Code and Guideline Changes: 99221-99233 descriptors, initial service rule, APP specialty rule and countable time (linked above). Accessed 18 Nov 2026.
- CMS, Medicare Claims Processing Manual, Chapter 12, sections 30.6.9.1 and 30.6.10: initial hospital care, modifier AI, consult codes, 99499 (linked above). Accessed 18 Nov 2026.
- CDC, ICD-10-CM browser FY2026: O60.02, O60.03 and Z3A codes (linked above). Accessed 18 Nov 2026.
Read about the author, or contact us with a question. See our editorial policy.
Last updated: 18 November 2026 · Educational content for U.S. billers. Check each payer’s current rules.