Yes. A preventive visit and sick visit same day with modifier 25 is allowed when the extra problem needs real, separate work. Bill the preventive code clean and add modifier 25 to the problem E/M.
Stable conditions that only get refills and routine labs stay in the preventive code. Bill the second visit only when a problem changes the plan or needs its own workup.
TL;DR: Report the preventive medicine code (99381-99397) without a modifier. Add an office visit code (99202-99205 or 99212-99215) with modifier 25 only when a new or existing problem needs significant extra work. Trivial problems are not billed. Medicare treats 99381-99397 as noncovered, and RHC Medicare rules pay most same-day medical encounters as one visit.
Written by Manikandan J, CPC, CRCR, a certified coder and revenue cycle specialist. Published 18 November 2026. Last updated: 18 November 2026.
Table of Contents
Can you bill a preventive visit and a sick visit on the same day?
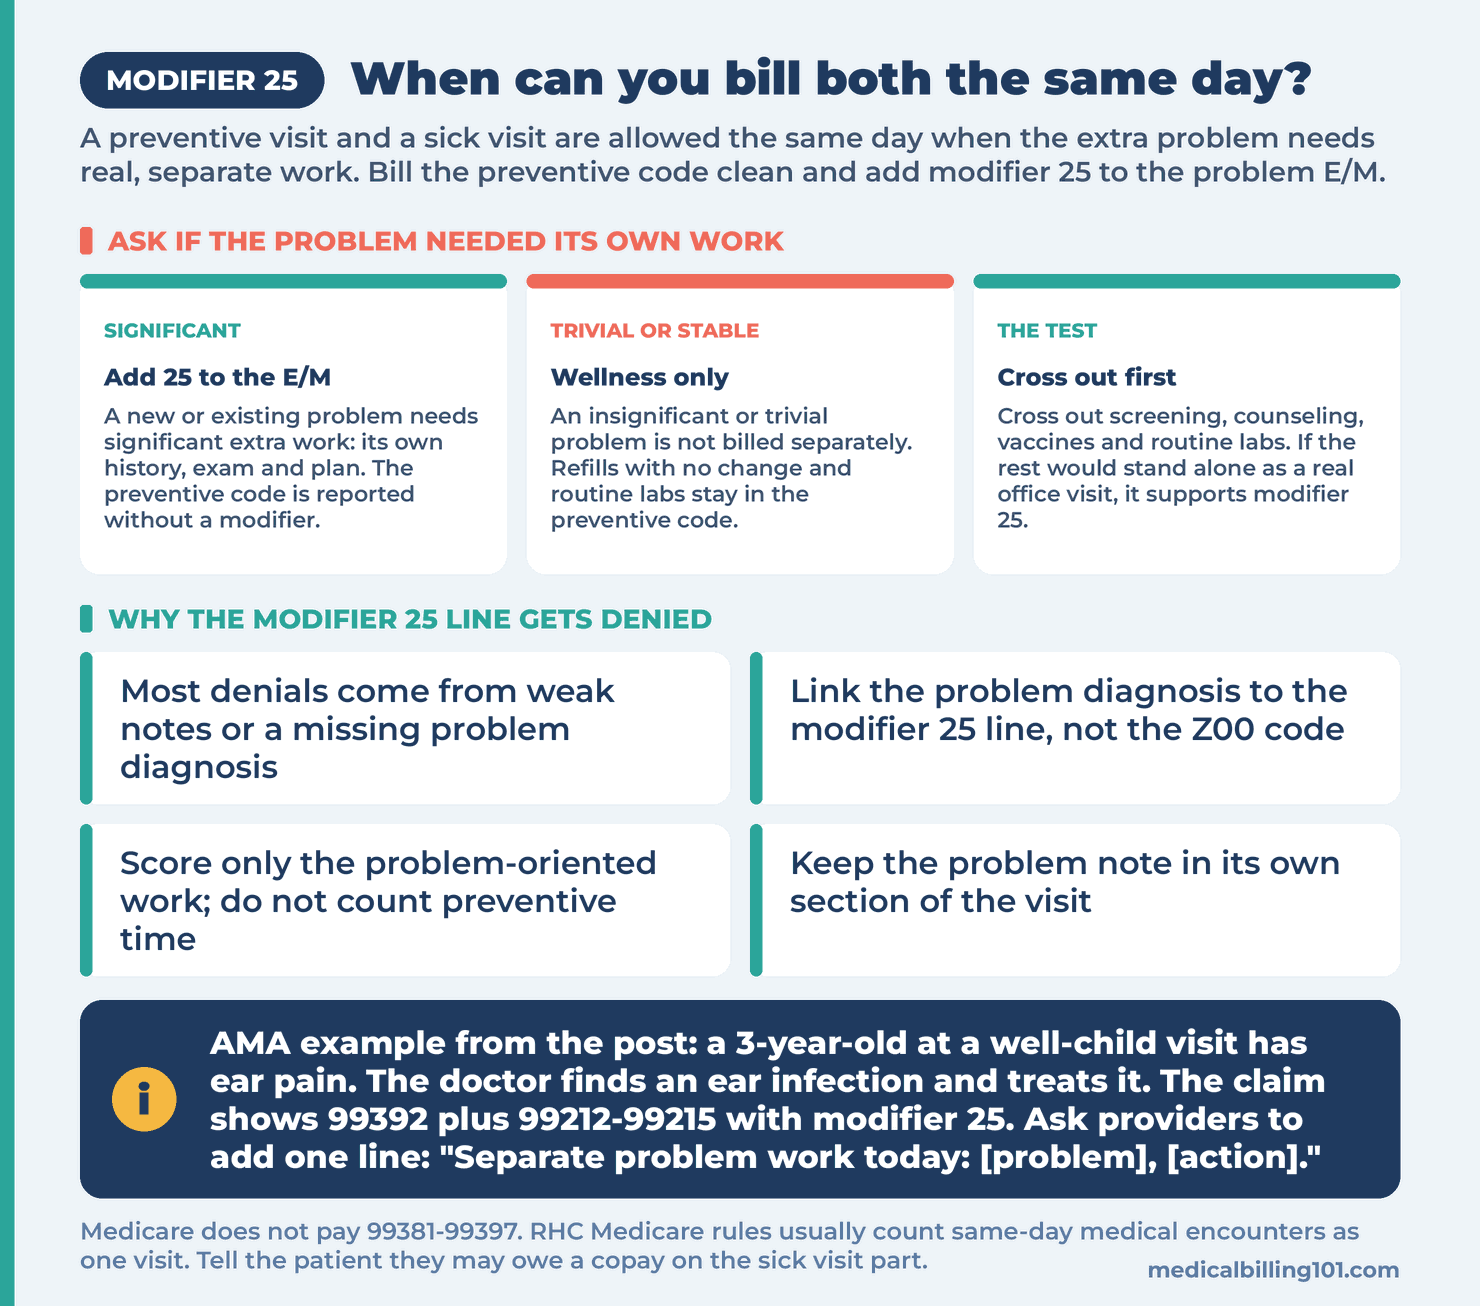
Modifier 25 is the CPT modifier for a significant, separately identifiable E/M service on the same day as another service. Yes, it applies when the problem is significant. The AMA guide to reporting CPT modifier 25 says to add an office visit code when a problem needs extra work to perform a problem-oriented E/M. The preventive code is reported without a modifier.
The same AMA guide gives the other half of the rule. An insignificant or trivial problem found during the preventive visit is not billed as a separate office visit. So do not ask if a problem was named. Ask if the problem needed its own history, exam and plan.
The AMA example is a 3-year-old at a well-child visit with ear pain. The doctor finds an ear infection and treats it. The claim shows 99392 for the preventive visit plus 99212-99215 with modifier 25 for the ear problem.
Do stable chronic conditions support a separate E/M at a physical?
Usually not. Preventive medicine services are the CPT wellness codes 99381-99397, sorted by new or established patient and age. They already include an age and gender appropriate history, exam, risk factor counseling and ordering of labs or tests. If a stable condition only gets a refill and routine labs, that work is part of the wellness visit. Bill a separate E/M only when the condition needs extra care.
A simple test helps. Cross out everything that is screening, counseling, vaccines and routine labs. Then look at what is left. If the rest would stand alone as a real office visit, it supports modifier 25. If nothing is left, bill the wellness code only.
- Stays in the preventive code. Refills with no change, screening mammogram orders, colon cancer screening review, routine lipid panel, vaccine counseling and family history review.
- Can support modifier 25. A dose change for uncontrolled blood pressure, a new symptom that needs a workup, an abnormal finding that needs a diagnostic order, or a new prescription for an acute problem.
- Gray area. A family history that leads to a gene test referral. Risk counseling is part of the wellness code, so write down what extra work was done.
Our modifier 25 and 59 helper walks through this same-day test step by step.
How do you pick the E/M level for the problem part?
Score only the problem-oriented work. Use MDM or total time, but count nothing that belongs to the preventive service. The AMA E/M guidelines say not to count time spent on other services that are reported separately. Preventive time is one of them.
Most problem add-ons land at 99212 or 99213. A 99214 needs moderate MDM, such as a drug change for a chronic illness that is getting worse. Our E/M level calculator scores the three MDM elements for you. Our E/M coding cheat sheet shows the full 2026 MDM table and time minimums.
| Claim line | Code | Modifier | Diagnosis pointer |
|---|---|---|---|
| Preventive visit (adult, established, age 40-64) | 99396 | None | Z00.00 or Z00.01 |
| Problem visit, if significant | 99212-99215 | 25 | The problem diagnosis, such as the uncontrolled condition |
| Vaccine and administration | Vaccine code plus admin code | None | Z23 |
Use Z00.01 when the exam finds an abnormal result, and code the finding too. Link the problem diagnosis to the modifier 25 line, not the Z00 code.
How does Medicare handle a preventive visit with a problem visit?
Medicare does not pay for 99381-99397. Per the Medicare Claims Processing Manual, Chapter 12, section 30.6.2, a covered visit at the same time is paid in place of part of the wellness visit. The patient may be billed the gap between the two charges.
The same section says an ABN is not required for the routine part, but CMS strongly urges one. Screening tests for patients with no symptoms are not covered. Tests ordered for a symptom or known condition are checked for need.
The annual wellness visit (AWV) is the Medicare yearly visit to plan prevention. It works differently. Per the CMS annual wellness visit page, you report G0438 or G0439 and add 99202-99205 or 99211-99215 with modifier 25 for a significant, separate, medically necessary E/M. G0438 is the first AWV and G0439 is each later one.
What changes for a rural health clinic (RHC)?
For Medicare, an RHC is paid per visit, not per code line. The Medicare Benefit Policy Manual, Chapter 13, section 40.3, says more than one medical visit on one day counts as one visit. An AWV on the same day as a medical visit is not a separately billable visit.
There are narrow exceptions. For RHCs, an initial preventive physical exam (G0402) plus a separate medical visit the same day can be two billable visits. A new illness or injury later the same day can also count, with modifier 25 or 59 on the RHC claim.
Commercial plans are a separate question. Many payer wellness-plus-sick policies leave out RHCs and FQHCs paid on flat visit rates. Read your contract before you pick the rule. An extra E/M may raise the doctor’s RVU credit but not clinic pay.
Will the patient owe a copay for the sick visit part?
Often, yes. Under 45 CFR 147.130(a)(2), a plan may impose cost sharing on an office visit when preventive items are billed separately, or when prevention is not the visit’s primary purpose. Many plans apply the deductible or copay to the modifier 25 line.
Tell the patient before the problem work starts. Surprise bills after a “free” physical cause most complaints. Our guide on being charged for an annual physical explains it from the patient side. You can also show the patient an estimate with our patient cost estimator.
Why do payers deny the modifier 25 line on a wellness claim?
Most denials come from weak notes or a missing problem diagnosis. Payers bundle the office visit into the wellness code when the note does not show separate work. A missing or misplaced modifier also triggers a CO-4 denial for an inconsistent modifier.
In my AR work, most denied modifier 25 lines on wellness claims pointed only to the Z00 code, with no problem diagnosis linked.
Keep the problem note in its own section of the visit. State the problem, what was done, and the decision made. The same separate-note habit fixes the denial in our answer on Aetna denying 99213 billed with an x-ray. Use the NCCI edit checker to see which code pairs need a modifier.
Ask providers to add one line to the assessment: “Separate problem work today: [problem], [action].” Coders can then split the claim in seconds. Auditors see the same reason the coder saw.
3-step checklist
- Cross out screening, counseling, vaccines and routine labs; see if a real problem visit remains.
- If it does, bill 99212-99215 with modifier 25, scored on the problem work only.
- Check Medicare, AWV, RHC and payer contract rules before the claim goes out.
FAQ
Can you bill a preventive visit and sick visit on the same day?
Yes, when the problem needs significant extra work. Bill the preventive code without a modifier and the office visit code with modifier 25.
Which code gets modifier 25, the preventive or the problem visit?
The problem visit. Append modifier 25 to 99202-99205 or 99212-99215. The preventive code 99381-99397 is reported without a modifier.
Do refills for stable conditions support a separate E/M at a physical?
Usually not. A refill with no change and routine labs are part of the preventive service. Extra management, such as a dose change, can support a separate visit.
Can you bill an E/M with the Medicare annual wellness visit?
Yes. CMS allows 99202-99205 or 99211-99215 with modifier 25 alongside G0438 or G0439 when the E/M is significant, separate and medically necessary.
Does an RHC get paid twice for a wellness visit and sick visit?
Not under Medicare in most cases. Same-day medical encounters count as one RHC visit, and an AWV with a medical visit is not separately billable. An IPPE plus a medical visit is an exception.
Sources
My methodology was simple. I checked the AMA modifier 25 guide and E/M guidelines, two CMS manuals, the CMS AWV billing page and the federal preventive cost-sharing rule. Commercial payers may apply their own rules, so check each payer’s policy.
- AMA, Reporting CPT Modifier 25: preventive medicine rule and pediatric 99392 example (linked above). Accessed 18 Nov 2026.
- AMA, CPT E/M Code and Guideline Changes: time excludes separately reported services (linked above). Accessed 18 Nov 2026.
- CMS, Medicare Claims Processing Manual, Chapter 12, section 30.6.2: covered visit with noncovered preventive service (linked above). Accessed 18 Nov 2026.
- CMS, Annual Wellness Visit coding and billing page: G0438, G0439 and modifier 25 (linked above). Accessed 18 Nov 2026.
- CMS, Medicare Benefit Policy Manual, Chapter 13, section 40.3 and RHC preventive services (linked above). Accessed 18 Nov 2026.
- eCFR, 45 CFR 147.130(a)(2): office visit cost sharing (linked above). Accessed 18 Nov 2026.
Read about the author, or contact us with a question. See our editorial policy.
Last updated: 18 November 2026 · Educational content for U.S. billers. Check each payer’s current rules.