

OA-136 comes from a secondary or later payer. It’s saying the primary plan denied or cut the claim because a rule wasn’t followed, so the secondary won’t step in to cover that gap. Think of a missed prior authorization, an out-of-network provider or a late claim on the primary. The secondary isn’t judging the care. It just won’t pay for a slip on the primary claim. X12 limits this code to group OA. (Primary source: X12 Claim Adjustment Reason Codes)
In brief: CARC 136 reads “Failure to follow prior payer’s coverage rules. (Use only with Group Code OA)” The fix lives on the primary claim. Find why the primary denied, fix or appeal it there, and then send the secondary a claim with the new primary results.
From our denial codes library. Written by Manikandan J, CPC, CRCR, who has worked coordination of benefits and secondary claims for hospital and physician billing teams. Published 21 October 2026. Last updated: 21 October 2026. Code wording quoted word for word from X12.
X12 entry for reason code 136
| Field | X12 text |
|---|---|
| Code | 136 |
| Description | “Failure to follow prior payer’s coverage rules. (Use only with Group Code OA)” |
| Start | 10/31/1998 |
| Last modified | 07/01/2013 |
Source: X12 Claim Adjustment Reason Codes, checked 21 October 2026.
How a secondary payer decides
Coordination of benefits is the process plans use to decide who pays first and how much the next plan adds. The primary payer is the plan that pays first. The secondary payer is the next plan in line. It looks at what the primary did. Then it pays some or all of what is left.
Most secondary plans won’t pay a balance that exists only because a rule was skipped. Medicare’s version of this sits in its coordination of benefits overview. Many commercial contracts say the same in their provider manuals.
| Primary result | What the secondary usually does |
|---|---|
| Paid, with patient cost share | Considers the deductible, coinsurance or copay |
| Denied as not covered | May review under its own benefits |
| Denied for a missed rule, such as no auth | Denies with OA-136 |
Example scenario (fictional names), part 1
OA-136 Denial Example: What Happened
Felipe Moreau bills for Northfield Imaging Center. A patient had a lumbar spine MRI without contrast, 72148, for low back pain with sciatica (M54.41). The primary plan denied it for no prior authorization. Felipe sent the claim to the secondary, Granite Shore Health, a fictional commercial plan.
The secondary’s 835 showed CAS*OA*136 for the full charge with remark LQ*HE*N36, “Claim must meet primary payer’s processing requirements before we can consider payment.”
Is the money gone, or is there still a path? Keep reading, or jump to how the OA-136 denial was resolved.
Remark codes that often travel with CARC 136
| RARC | X12 wording |
|---|---|
| N36 | “Claim must meet primary payer’s processing requirements before we can consider payment.” |
| MA04 | “Secondary payment cannot be considered without the identity of or payment information from the primary payer. The information was either not reported or was illegible.” |
| N4 | “Missing/Incomplete/Invalid prior Insurance Carrier(s) EOB.” |
The full list is on the X12 RARC page.
How to fix an OA-136 denial
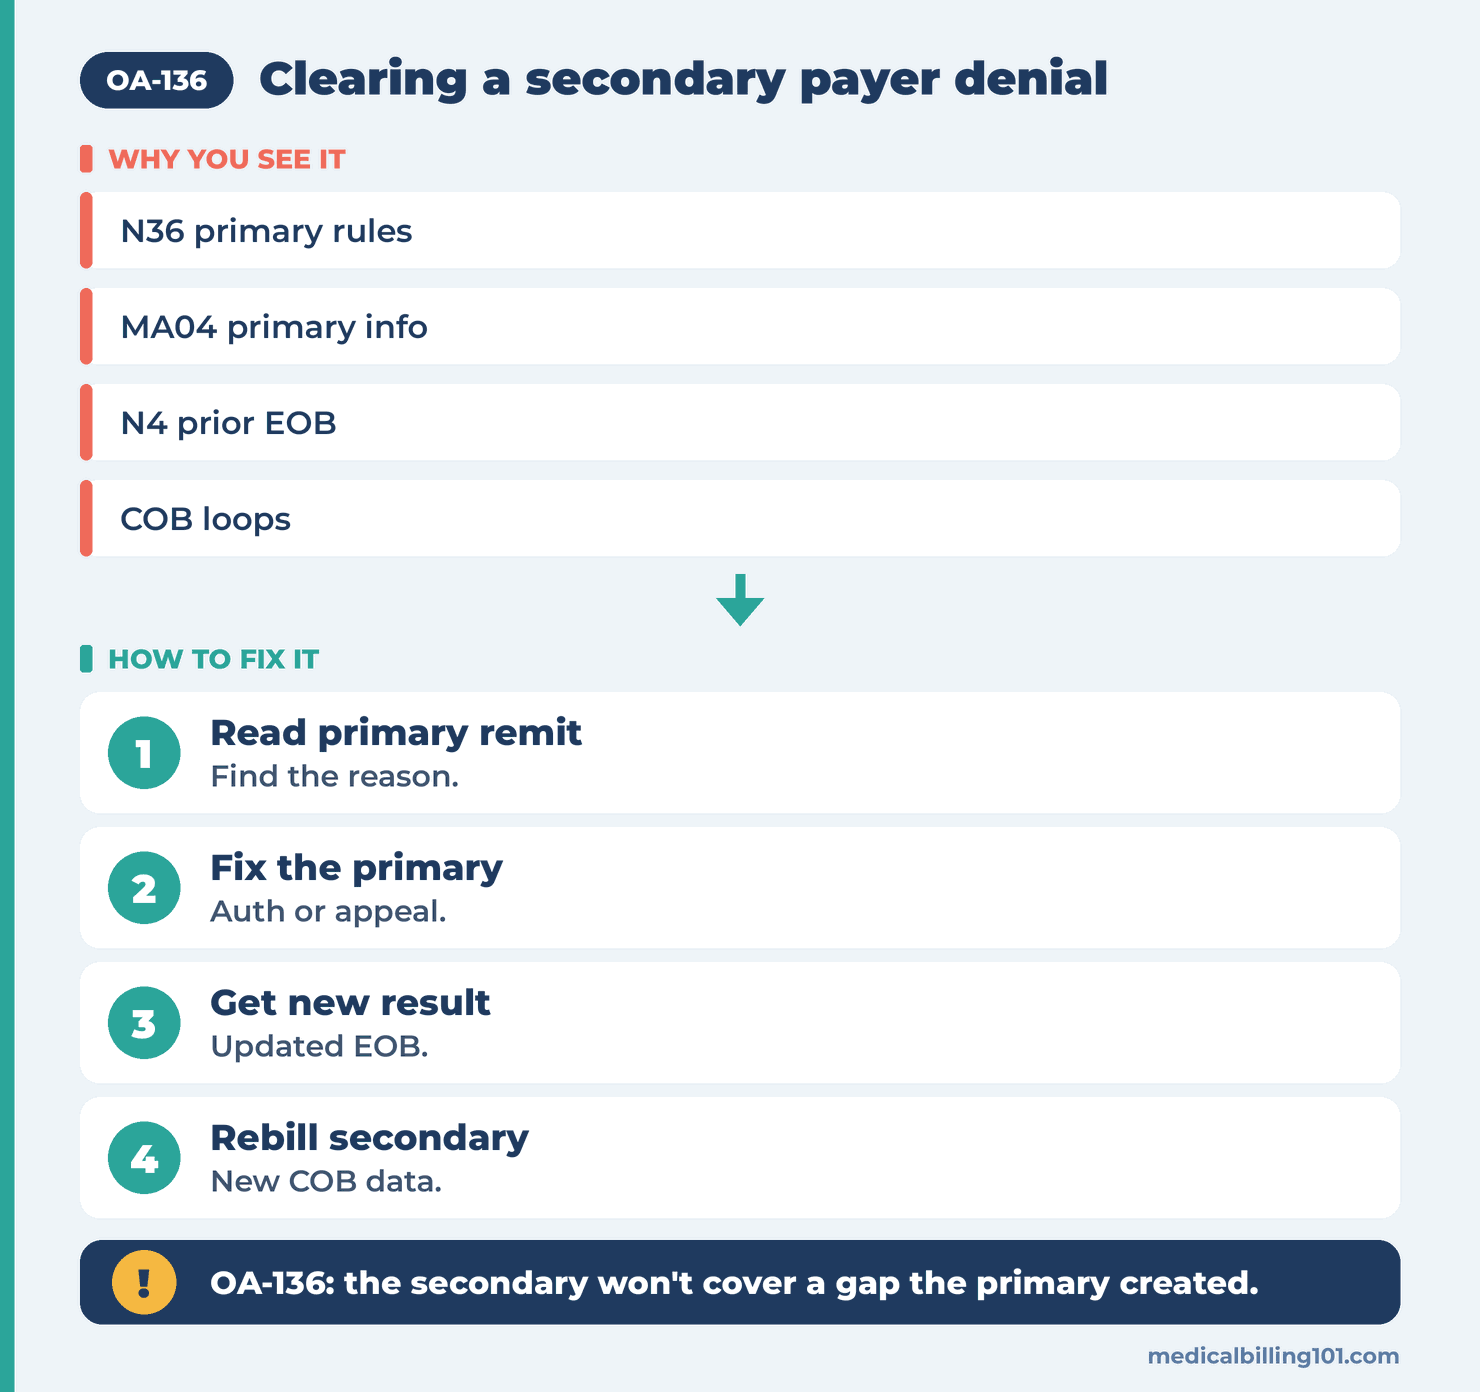
- Pull the primary remit. Read the primary’s group code, CARC and RARC. For example, CO-197 means the primary wanted an authorization.
- Fix the primary problem first. Ask for a retro authorization, file a primary appeal or send a corrected claim, such as one with a missing referral number.
- Wait for the new primary result. The secondary needs the updated primary payment and adjustments.
- Rebill the secondary. Include the new primary amounts in the 837 COB loops, or attach the new EOB on paper claims.
- If the primary can’t be fixed, check your contract. The balance is often a provider write-off, not a patient bill.
- Prevent repeats. Check both plans’ auth rules at scheduling, not just the primary’s.
Example scenario (fictional names), part 2
How the OA-136 Denial Was Resolved
Felipe called the primary plan. Its policy allowed a retro authorization request within a set window after the scan. He sent the order, the physical therapy notes and the exam findings.
Fix: the primary approved the request. Felipe sent the primary a corrected claim with frequency code 7 and the new auth number, and it paid. He then billed the secondary with the primary’s payment and patient share in the COB loops.
Outcome: the secondary paid its part of the coinsurance. Northfield now checks auth rules for every plan on file at scheduling.
Names and details are illustrative; no real patient data.
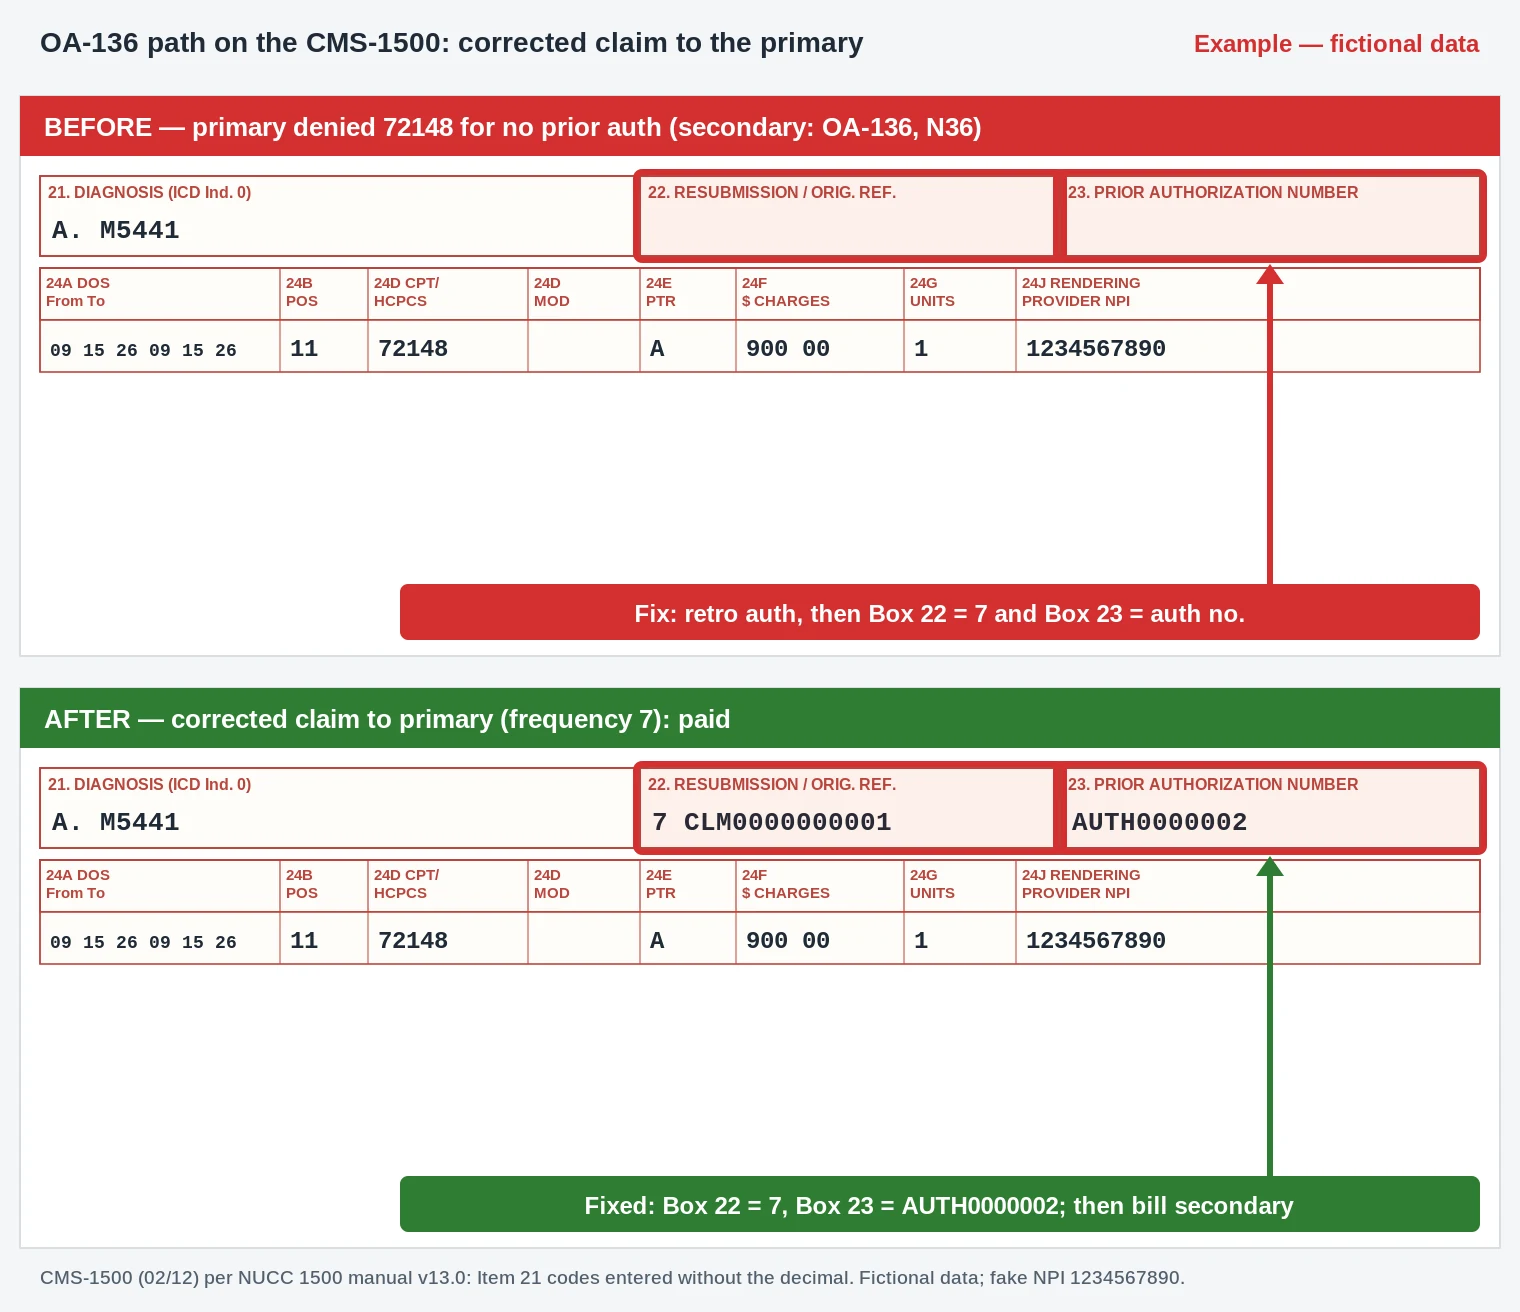

- Box 23 / FL 63: the primary’s retro authorization number added.
- Box 22 / FL 4 + FL 64: frequency code 7 with the primary’s original claim number (type of bill 0137 on the UB-04).
- Secondary claim: billed after the primary paid, with the primary’s payment and patient share in the 837 COB loops (FL 50 line B on the UB-04).
Worked example (illustrative)
A physical therapy clinic sees a patient whose primary plan requires an in-network provider. The clinic is out of network with the primary, which denies the claim. The secondary denies with OA-136. The clinic can’t change its network status after the fact, so it reviews the patient’s signed financial policy and its contracts before deciding whether any balance can go to the patient.
Who owes the balance after OA-136?
| Situation | Usual result |
|---|---|
| Primary rule fixed and claim paid | Secondary reconsiders the cost share |
| Provider missed the rule and can’t fix it | Usually a provider write-off under the contract |
| The patient chose to skip the rule after being told | May be billable if the plan and state law allow it and you have signed notice |
Related codes
- CO-197: precertification or authorization absent.
- CO-22: this care may be covered by another payer per coordination of benefits.
- CO-23: impact of prior payer adjudication.
- PR-242: services not provided by network or primary care providers.
Key takeaways
OA-136 is a secondary payer saying the primary rules weren’t followed. The fix is on the primary claim: find the reason, fix or appeal it, then rebill the secondary with the new results. If the primary can’t be fixed, check your contract before billing the patient.
FAQ
What does denial code OA-136 mean?
A later payer won’t pay because the prior payer’s rules weren’t followed. It reads “Failure to follow prior payer’s coverage rules.”
Is CARC 136 a primary or secondary payer code?
It comes from a secondary or later payer. It reacts to how the primary handled the claim.
Can I bill the patient after an OA-136 denial?
Usually not when the provider missed the rule. Check your contracts, state rules and any signed notice.
How do I fix reason code 136?
Fix the primary claim first, for example with a retro authorization or appeal. Then rebill the secondary with the new primary results.
Why does OA-136 use the OA group?
X12 allows it only with group OA. The adjustment comes from the prior payer’s action, not this payer’s contract.
What does N36 mean with CARC 136?
The claim must meet the primary payer’s rules before the secondary will look at it.
Sources
How we checked: each code quote on this page was matched word for word with the X12 CARC and RARC lists on 21 October 2026.
- X12, Claim Adjustment Reason Codes (CARC 136, 22, 23, 197, 242). Accessed 21 Oct 2026.
- X12, Remittance Advice Remark Codes (N36, MA04, N4). Accessed 21 Oct 2026.
- CMS, Coordination of benefits and recovery overview. Accessed 21 Oct 2026.
Last updated: 21 October 2026 · Educational content; not legal advice.