

The CO-B12 denial code means the payer reviewed the patient’s medical record and could not find the service, or all of the units, that the claim billed. It usually follows a records request or a documentation audit. Your decision is straightforward: correct the claim to what the clinical note supports, or appeal with documentation the reviewer overlooked. (Primary source: X12 Claim Adjustment Reason Codes)
In brief: reason code B12 is a documentation finding, not a coding rule. Compare the note line by line with the claim. If the note was complete but never reached the payer, appeal. If the claim billed more than the note shows, correct the claim.
Part of our denial codes library. Written by Manikandan J, CPC, CRCR, who has worked therapy and clinic denials after payer record reviews found units the notes did not support. Published 18 November 2026. Last updated: 18 November 2026. Code wording quoted word for word from X12. Read about the author and our editorial policy, or contact us to report an error.
What does denial code CO-B12 mean?
Denial code CO-B12 says the record does not back up the billed service. Payers send it after they request notes, for example during a prepayment review, a post-payment audit or a routine records request. Timed therapy codes, procedures billed with a visit, and extra units are common targets.
| Field | Value |
|---|---|
| Code | B12 |
| Description | “Services not documented in patient’s medical records.” |
| Group codes | No X12 group restriction; CO is the usual pairing |
| Start | 01/01/1995 (last modified 03/01/2018) |
| Common remarks | N237, M127 |
Source: X12 Claim Adjustment Reason Codes, checked 18 November 2026.
Methodology: the code wording is copied from the X12 list, and the timed-unit rules come from the CMS therapy billing chapter cited below.
Key terms: a timed code is a CPT code billed per 15 minutes of direct treatment. Units are the count in Box 24G or FL 46. A records request is the payer’s letter asking for notes before or after payment.
CO-B12 or OA-B12: which one did you get?
| Group | Who carries the amount | What to do |
|---|---|---|
| CO-B12 | Your practice, as a contractual write-off; the patient is not billed | Correct or appeal |
| OA-B12 | No one is named, often when a second payer repeats the first payer’s finding | Check the primary remit, then correct or appeal |
Example scenario (fictional names), part 1
CO-B12 Denial Example: What Happened
Nadia Haddad bills for Brookstone Physical Therapy. Liam Castellanos, a physical therapist, treated a patient for right knee osteoarthritis, M17.11. The claim listed 97110 with modifier GP for four units and 97140-GP for one unit.
After a records request, the 835 from a fictional commercial payer denied the 97110 line. It showed CAS*CO*B12 with remark code N237, “Incomplete/invalid patient medical record for this service.” The note was signed, dated and sent on time.
So what part of the record did the reviewer say was missing? Keep reading, or jump to how the CO-B12 denial was resolved.
How do I find what the record is missing?
Read the note the way a payer reviewer would. Confirm that every billed line has a matching clinical entry, then verify the documented treatment time against the billed units. The CMS therapy billing chapter explains how total timed minutes convert to units.
| Total timed minutes | Units allowed |
|---|---|
| 8 to 22 | 1 |
| 23 to 37 | 2 |
| 38 to 52 | 3 |
| 53 to 67 | 4 |
| 68 to 82 | 5 |
Missing signatures, undated entries and notes attached to the wrong date of service also produce B12 findings. So does a separately billed procedure, such as a joint injection, that the visit documentation never describes.
How do I fix a CO-B12 denial?
To fix a CO-B12 denial, decide whether the claim or the submission was wrong. Never add notes after the fact to support a claim. A late entry must be dated when it was written and must reflect what really happened.

| Situation | Fix | Proof |
|---|---|---|
| Claim billed more than the note shows | Corrected claim with supported units or codes, Box 22 code 7 | The note itself |
| Note was complete but not sent | Appeal with the full note | Signed, dated note |
| Wrong patient or wrong date in the packet | Appeal with the right record | Correct note and a cover letter |
| No note exists | Write off the line | None |
The CMS Program Integrity Manual, Chapter 3 describes how Medicare reviewers judge signatures and documentation. Many commercial plans follow similar rules.
Example scenario (fictional names), part 2
How the CO-B12 Denial Was Resolved
Nadia added up the minutes in Liam’s note. Here is what she found:
- The note showed 40 minutes of 97110 and 15 minutes of 97140.
- That is 55 timed minutes, which supports four units in total, not five.
- Under the CMS method, 97110 gets three units and 97140 gets one.
Fix: she sent a corrected claim with code 7 in Box 22 and the original claim number. Box 24G for 97110-GP dropped from 4 to 3. M17.11 and the 97140 line stayed the same.
Outcome: the payer paid three units of 97110. Nadia set up a charge check that compares billed units with total timed minutes.
Names and details are illustrative; no real patient data.
Names and details are illustrative; no real patient data.
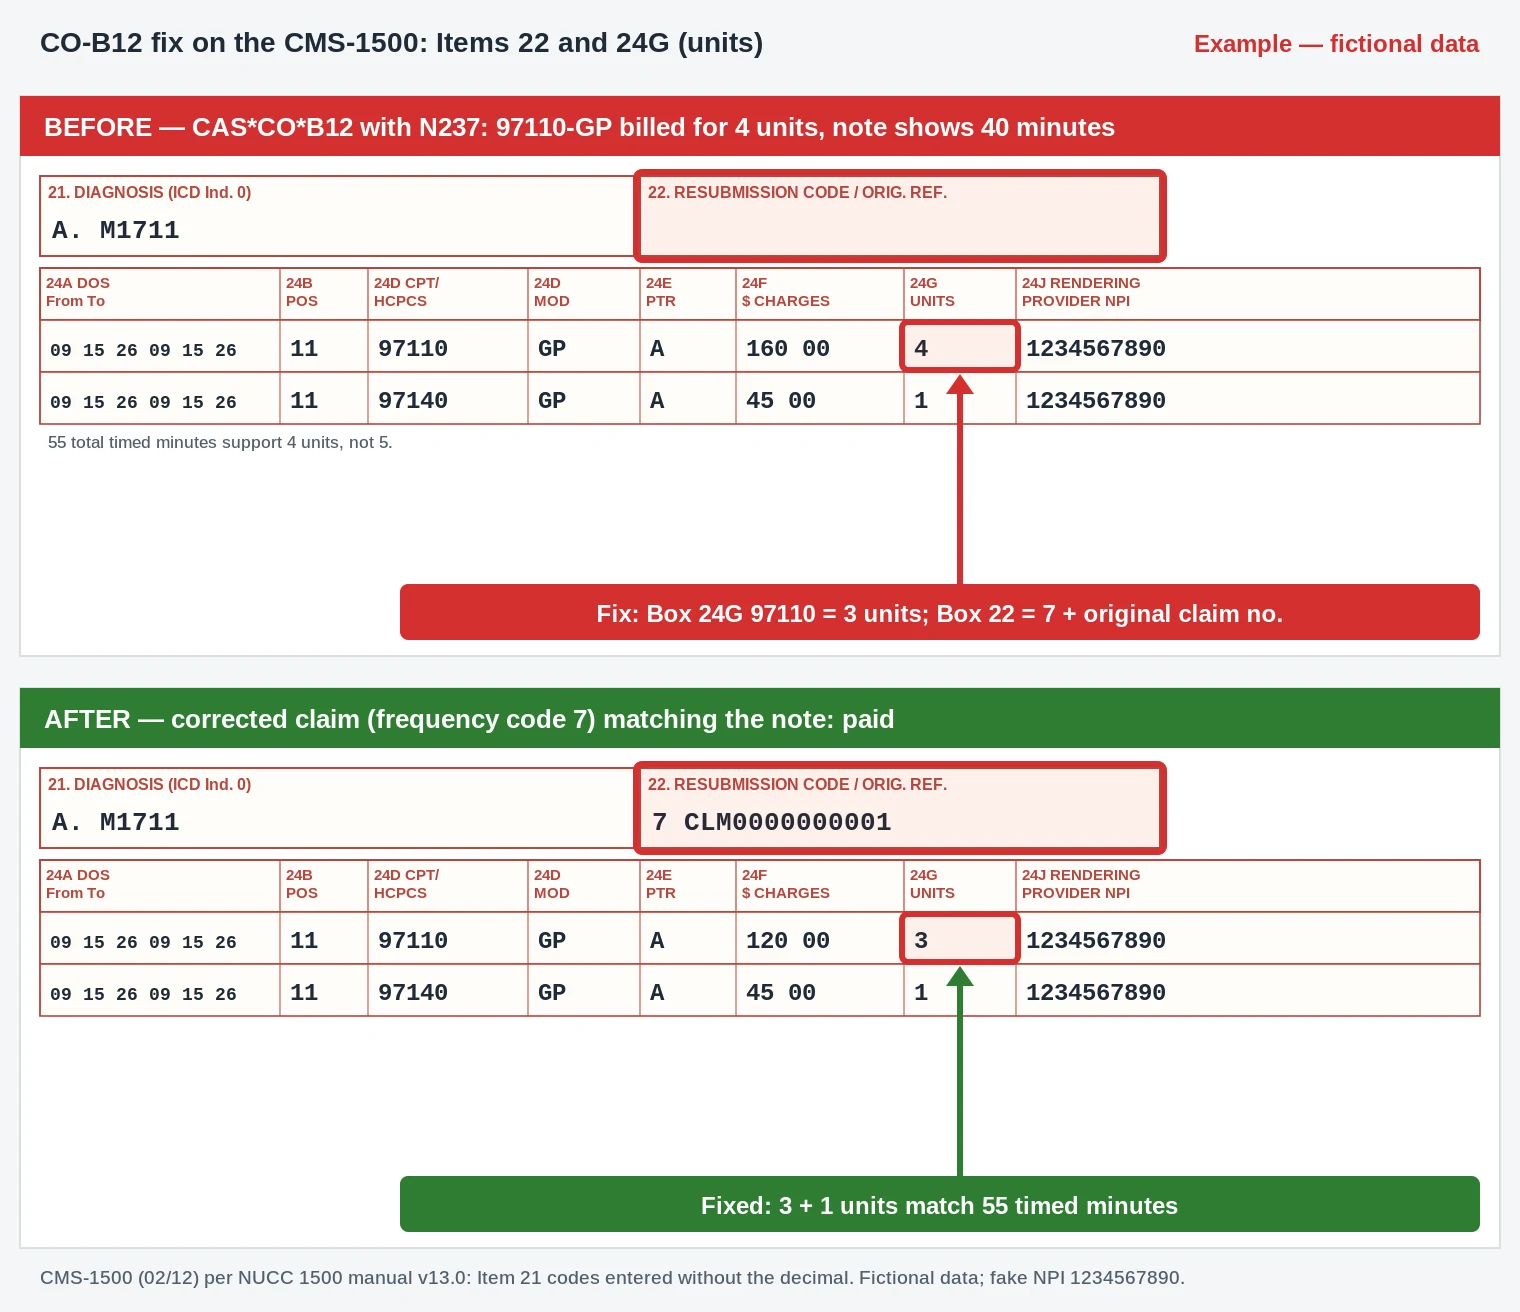
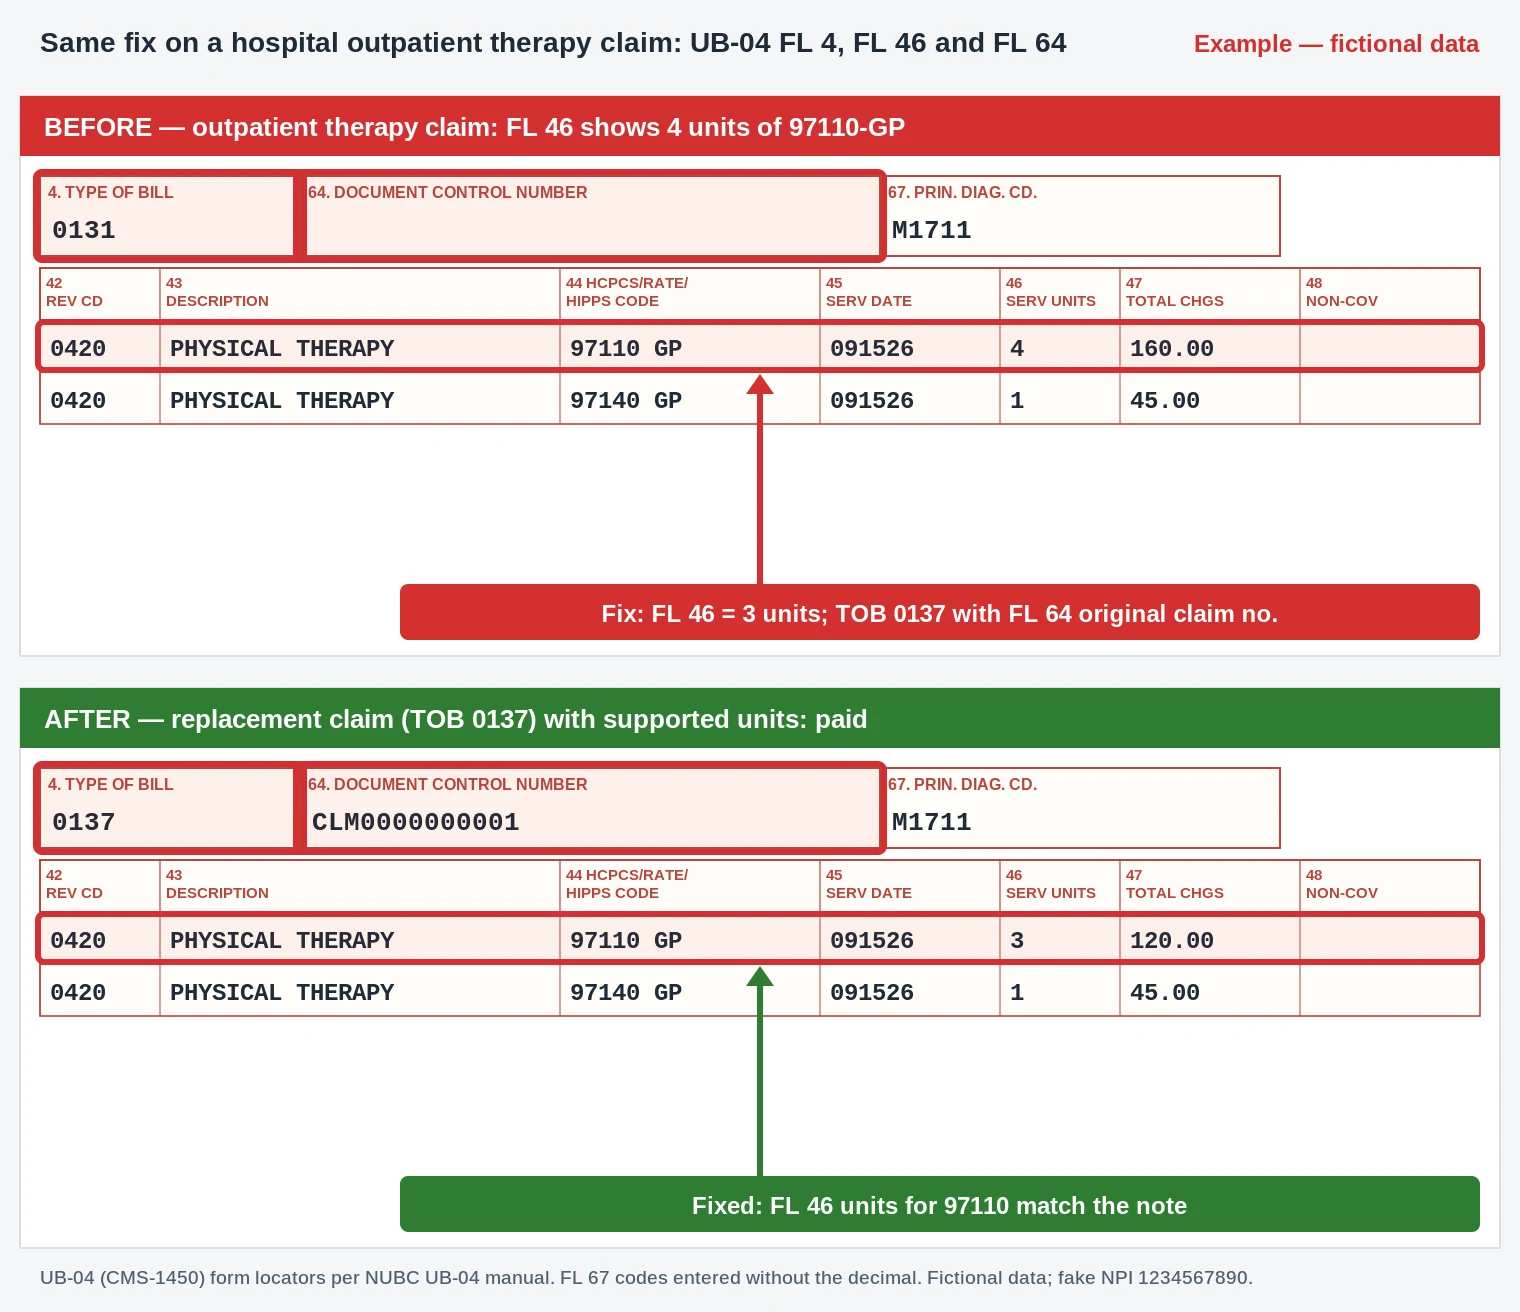
- Box 24G / FL 46: 97110-GP units reduced from 4 to 3, because 55 total timed minutes support 4 units in all (3 for 97110, 1 for 97140).
- Box 24F / FL 47: the line charge follows the new unit count (amounts are placeholders).
- Box 22 / FL 4 + FL 64: frequency code 7 with the original claim number (bill type 0137 on the UB-04).
- Box 21 / FL 67: M17.11 (entered as M1711) and the 97140-GP line are unchanged.
Can I bill the patient for a CO-B12 denial?
No. The CO group code makes the denied amount a contractual provider write-off. The patient owes only the deductible, copayment or coinsurance on lines the payer actually allowed.
How do I prevent CARC B12?
Prevent it by reviewing documentation before claims are released. Build a charge rule that totals timed minutes and flags any claim with more units than the documented minutes allow. Hold charges until the treating clinician signs the note. For example, a clinic that bills from the schedule instead of the note will keep seeing B12.
Related codes
| Code | Meaning |
|---|---|
| CO-150 | Information submitted does not support this level of service |
| CO-151 | Information does not support this many services |
| CO-252 | An attachment or other documentation is required |
| CO-50 | Service not deemed a medical necessity by the payer |
FAQ
What does CO-B12 mean?
The payer found that the medical record does not show the service or units the claim billed.
Should I appeal or correct a CO-B12 claim?
Correct it if the claim billed more than the note supports. Appeal if a complete note was missed.
Can I add a note to fix CARC B12?
Only a properly dated late entry that reflects real care. Never create documentation to fit a claim.
Which remark codes come with B12?
N237 or M127 are common, depending on whether the record was incomplete or missing.
Which group code comes with CARC B12?
X12 sets no group restriction. CO is the most common pairing.
Sources
How we checked: the CARC B12 quote was matched word for word with the X12 CARC list on 18 November 2026, and N237 and M127 with the X12 RARC list.
- X12, Claim Adjustment Reason Codes (CARC B12, 150, 151, 252). Accessed 18 Nov 2026.
- X12, Remittance Advice Remark Codes (N237, M127). Accessed 18 Nov 2026.
- CMS, Medicare Claims Processing Manual, Chapter 5 (outpatient therapy billing). Accessed 18 Nov 2026.
- CMS, Medicare Program Integrity Manual, Chapter 3 (medical review). Accessed 18 Nov 2026.
- NUCC, 1500 claim form reference instruction manual. Accessed 18 Nov 2026.
Last updated: 18 November 2026 · Educational content; not legal advice.