

CARC 101 is the code a payer uses when it answers a request for an estimate. It tells you what the plan expects to pay once the care is done and a real claim comes in. No money moves. A predetermination is a payer’s written estimate of what it would pay for planned care. It’s based on the plan as it stands on the day of the review. People mix it up with prior approval, and that’s where most trouble starts. An estimate isn’t approval. It isn’t a promise to pay. (Primary source: X12 Claim Adjustment Reason Codes)
In brief: CARC 101 is an estimate, not a payment. Treat the amount as a planning number for the patient. Check if the plan also needs prior approval. Then send a normal claim after the visit.
Part of our denial codes library. Written by Manikandan J, CPC, CRCR, who has handled pre-service requests for surgery practices. Published 21 October 2026. Last updated: 21 October 2026. Code wording is quoted word for word from X12.
The official X12 entry
| Field | X12 text |
|---|---|
| Code | 101 |
| Description | “Predetermination: anticipated payment upon completion of services or claim adjudication.” |
| Start | 01/01/1995 |
| Last modified | 02/28/1999 |
Source: X12 Claim Adjustment Reason Codes, checked 21 October 2026. You’ll most often see it under group OA, since nothing is being paid, denied or moved to the patient yet.
Example scenario (fictional names), part 1
OA-101 Denial Example: What Happened
Nora Lindqvist books surgery and does billing at Westbrook Plastic Surgery. Dr. Felix Amaro planned a panniculectomy, 15830, for a patient with loose belly skin after major weight loss (L98.7). Nora asked Fairmont Health Plan, a fictional commercial plan, for an estimate.
The 835 that came back showed CAS*OA*101 with an allowed amount and remark LQ*HE*N183. Nora booked the surgery and told the patient what to expect.
Six weeks later, the claim for the same surgery was denied for no authorization. How did an OA-101 reason code with a dollar figure turn into a denial?
What did the predetermination never say? Keep reading, or jump to how the OA-101 denial was resolved.
Predetermination vs prior authorization
Prior authorization is the plan’s required OK before a listed service, such as surgery or a scan. These two get mixed up all the time. The table shows why that costs money.
| Predetermination (CARC 101) | Prior authorization | |
|---|---|---|
| What it answers | What the plan would likely pay | Whether the service may be done and paid |
| Required? | Usually optional | Required when the plan lists the service |
| Binding? | No; an estimate based on current info | Yes, within its terms and dates |
| Typical remit response | CARC 101 with no payment | Not on a remit; an auth number |
| What happens if you skip it | Nothing, but the patient has less certainty | The claim can be denied, such as CO-197 |
HealthCare.gov notes that even prior approval isn’t a promise the plan will cover the cost. An estimate promises even less.
Remark codes that travel with CARC 101
| RARC | X12 wording |
|---|---|
| N183 | “Alert: This is a predetermination advisory message, when this service is submitted for payment additional documentation as specified in plan documents will be required to process benefits.” |
| N133 | “Alert: Services for predetermination and services requesting payment are being processed separately.” |
| N915 | “Predetermination of services is not allowed under the member’s plan.” |
N133 matters when one claim mixes done and planned services. N915 means the plan doesn’t offer estimates at all, so call the plan instead.
How to use a CARC 101 response

- Read it as an estimate. Note the allowed amount, the patient share and any remark codes.
- Check the plan’s prior approval list. If the service needs approval, ask for it now. The estimate doesn’t replace it.
- Match the details. Codes, units, place of service and provider on the estimate should match what you’ll bill.
- Share it with care. Tell the patient it’s an estimate. It can change with coverage, the deductible and the final claim.
- Bill a normal claim after the service. Don’t mark it as a replacement for the predetermination.
- Send the papers N183 asks for. For example, attach notes or photos the plan lists, with the claim, not later.
Example scenario (fictional names), part 2
How the OA-101 Denial Was Resolved
Nora pulled the plan’s manual. N183 said more papers would be needed with the claim. Fairmont’s list also needed prior approval for 15830. Nora had read the estimate as approval.
Fix: Fairmont allowed a retro authorization request within its time limit. Nora sent the request with photos and notes on the skin problems. Once approved, she sent a corrected claim with frequency code 7 and the auth number.
Outcome: the claim paid close to the estimate. Westbrook’s checklist now has one line for the estimate and one for the approval.
Names and details are illustrative; no real patient data.
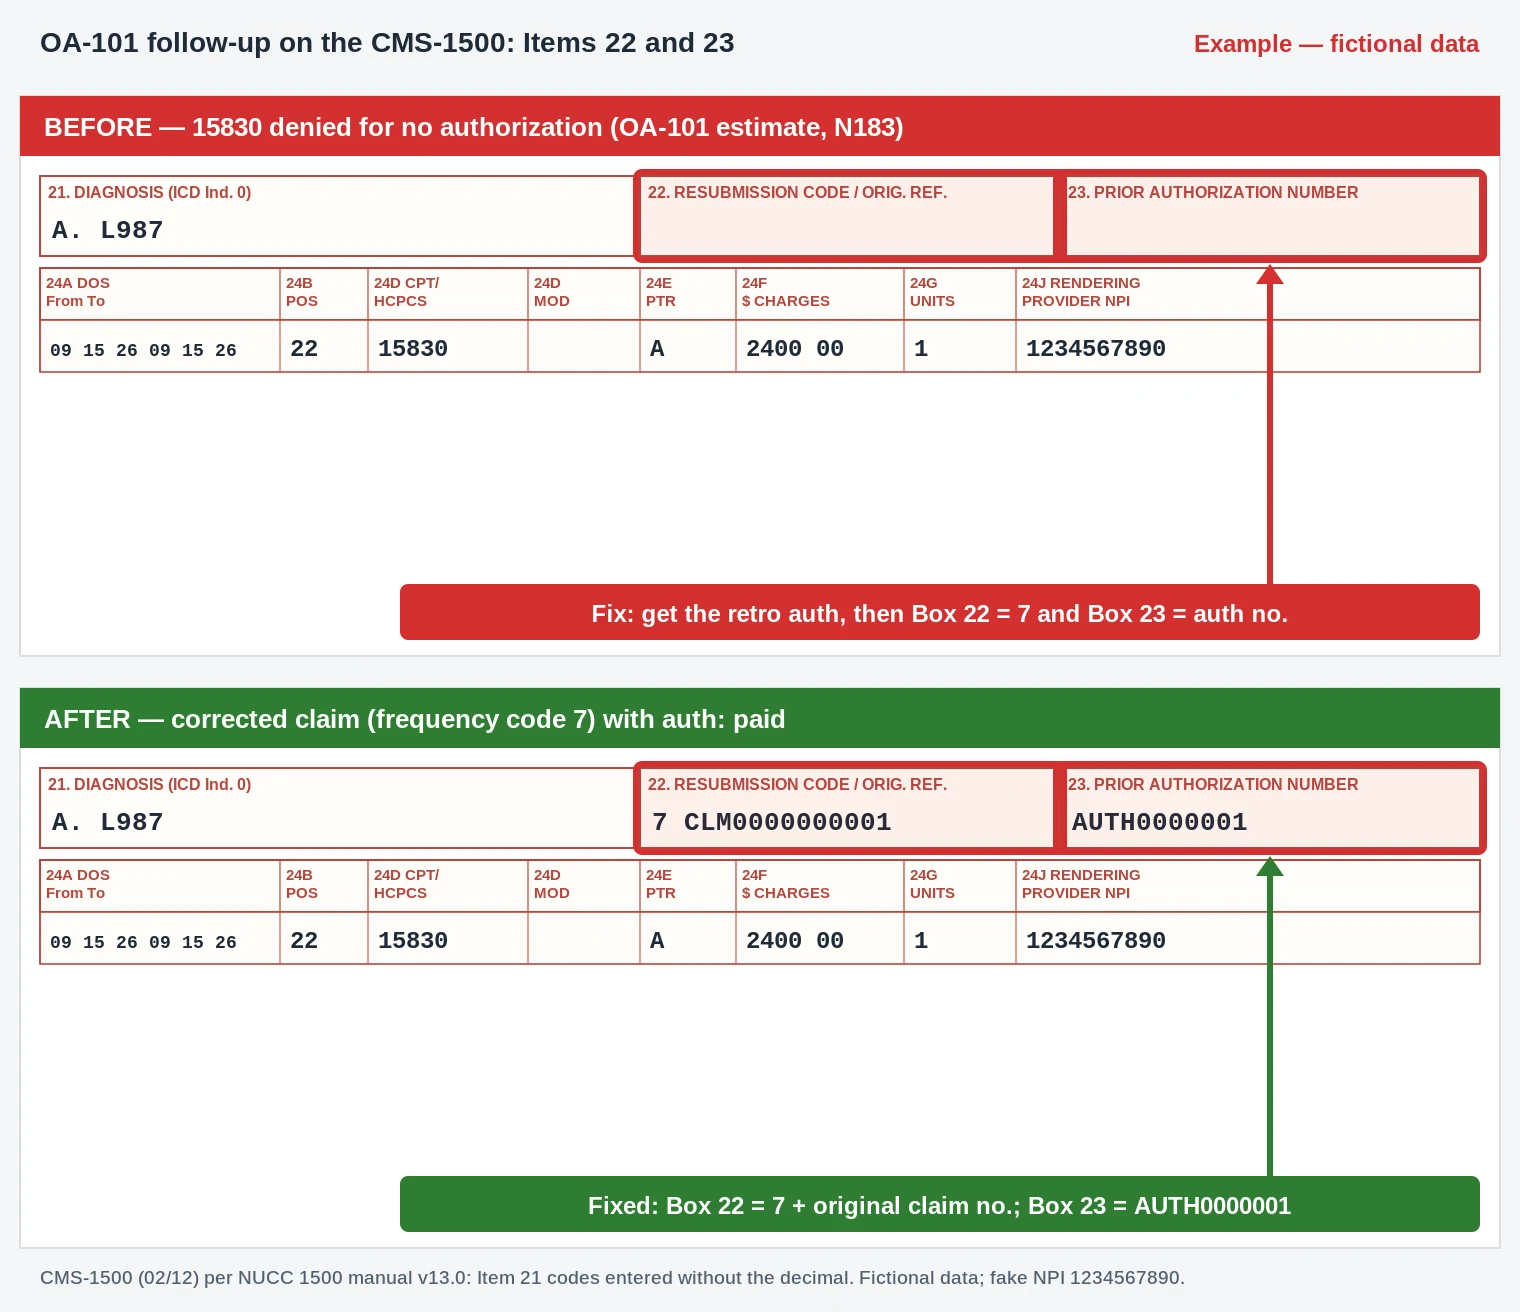
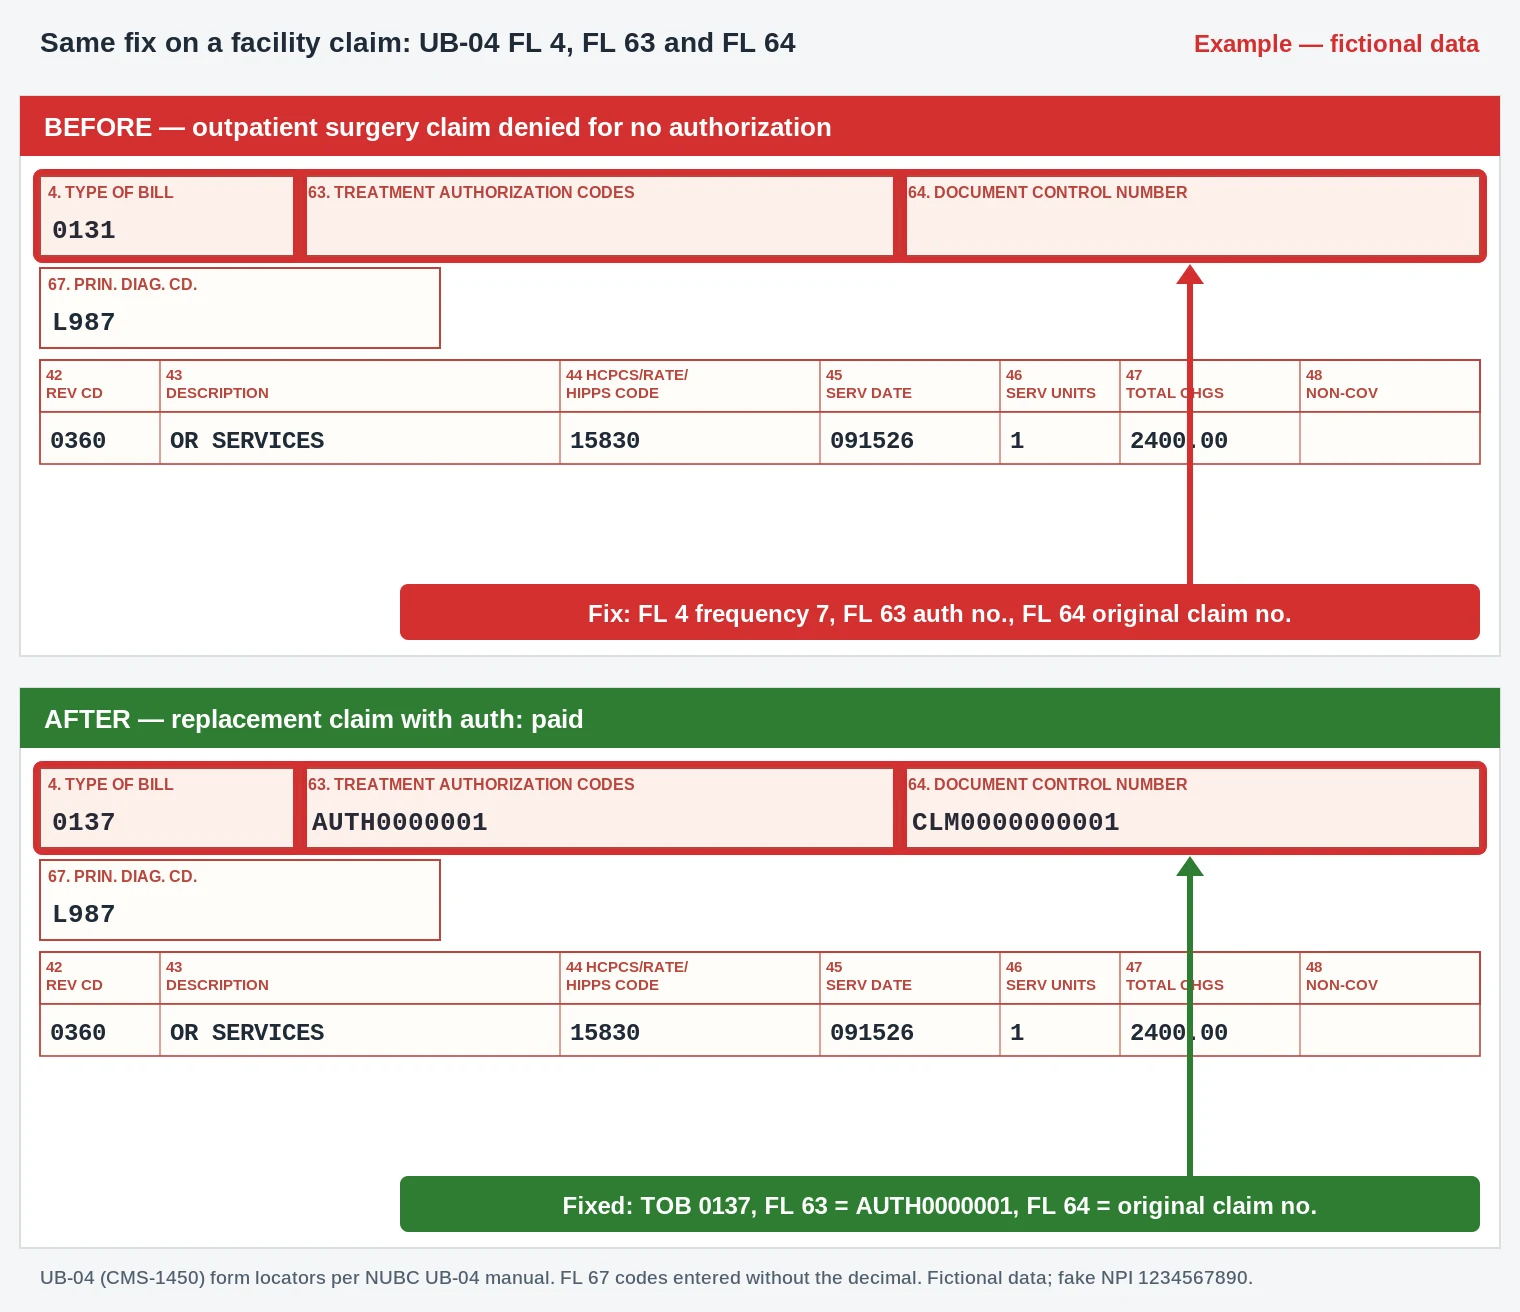
- Box 22 / FL 4 + FL 64: resubmission code 7 (corrected claim) with the original claim number. On the UB-04 the 7 is the last digit of the type of bill (0137).
- Box 23 / FL 63: the retro authorization number Fairmont approved.
- Box 24D / FL 44: 15830 and L98.7 (Box 21A / FL 67, entered as L987) are unchanged.
Worked example (illustrative)
An oral surgery office asks a medical plan to estimate benefits for removal of impacted teeth under general anesthesia. The response shows CARC 101 for the surgery and N915 for the anesthesia line. The office calls the plan and learns the anesthesia needs its own review. It requests that review, books the case, and tells the patient which part is still uncertain.
Common mistakes with predeterminations
- Using an old estimate. Benefits reset when the plan renews. Check again if the date falls in a new plan year.
- Changing codes after the estimate. If the surgeon adds a procedure, the estimate no longer covers the case.
- Quoting the estimate as a final price. Patients remember numbers. Label every quote as an estimate.
- Posting CARC 101 as a payment or write-off. Nothing happened to the balance; there isn’t one yet.
Related codes
- CO-197: precertification or authorization absent.
- CO-95: plan procedures not followed.
- CO-50: not deemed a medical necessity.
Key takeaways
OA-101 is an estimate of benefits, not a payment and not an approval. Check prior authorization separately, keep the codes on the estimate and the claim the same, and treat the dollar figure as a planning number for the patient. When the service is done, send a normal claim with the papers the plan asked for.
FAQ
What does CARC 101 mean?
It’s the code for an estimate. The plan is telling you what it expects to pay once the claim comes in.
Is a predetermination the same as prior authorization?
No. An estimate tells you what the plan might pay. Prior approval is a must for listed services.
Does OA-101 guarantee payment?
No. Payment depends on eligibility, benefits and the claim when it’s processed.
Should I post CARC 101 on the patient account?
No dollars move, so there’s nothing to post as paid or adjusted. Keep the response in the account notes.
What does N915 mean with a predetermination?
N915 means the plan doesn’t give estimates. Call the plan for a benefits check instead.
How long is a predetermination good for?
It depends on the plan. Most estimates assume the plan year and benefits in force at the time; check the response letter.
Sources
How we checked: each code quote on this page was compared word for word with the X12 CARC and RARC lists on 21 October 2026.
- X12, Claim Adjustment Reason Codes (CARC 101, 197). Accessed 21 Oct 2026.
- X12, Remittance Advice Remark Codes (N183, N133, N915). Accessed 21 Oct 2026.
- HealthCare.gov, Preauthorization (glossary). Accessed 21 Oct 2026.
Last updated: 21 October 2026 · This page is educational and doesn’t replace payer contracts or plan documents.