

CO-96 is a Claim Adjustment Reason Code that means the payer treated the charge as not covered, and the CO group code puts the amount on the provider, not the patient. (Primary sources: X12 Claim Adjustment Reason Codes · CMS Medicare Claims Processing Manual, Ch. 22 · CMS Ch. 30, ABN)
In brief: CO-96 means “non-covered charge(s).” The payer won’t pay the line, and because the group code is CO, you can’t bill the patient for it. The remark code next to 96 tells you why. Fix it if the code, diagnosis or claim format was wrong. Appeal if the service is a covered benefit. Otherwise, write it off.
Part of our denial codes library. Written by Manikandan J, CPC, CRCR, who has more than 10 years of US medical billing and revenue cycle experience. Published 6 October 2026. Last updated: 20 October 2026. Code wording is quoted word for word from X12. Medicare rules link to their CMS or Medicare contractor source.
CO-96 denial code description (official X12 wording)
X12 Claim Adjustment Reason Code 96, verbatim:
| Field | Official X12 text |
|---|---|
| Description | “Non-covered charge(s). At least one Remark Code must be provided (may be comprised of either the NCPDP Reject Reason Code, or Remittance Advice Remark Code that is not an ALERT.)” |
| Usage | “Refer to the 835 Healthcare Policy Identification Segment (loop 2110 Service Payment Information REF), if present.” |
Source: X12 Claim Adjustment Reason Codes, checked 20 October 2026. Start: 01/01/1995 | Last Modified: 07/01/2017.
Two parts of that text matter in practice. First, X12 requires a remark code with CARC 96, so a CO-96 line without one is incomplete and worth a call to the payer. Second, the usage note points you to the policy reference in loop 2110 REF, which often names the exact plan rule behind the denial.
Example scenario (fictional names), part 1
CO-96 Denial Example: What Happened
- Setting: Ken Okafor works denials for Birchwood Dermatology. Dr. Lena Marsh removed a changing mole from a patient’s back.
- Claim as billed: 11402 (benign lesion excision, trunk, 1.1 to 2.0 cm) with diagnosis Z41.1, “Encounter for cosmetic surgery,” sent to Riverbend Health, a fictional plan.
- Denial on the 835:
CAS*CO*96withLQ*HE*N569, “Not covered when performed for the reported diagnosis.”
A CO-96 denial code on a medically needed excision. Was the service really non-covered, or was something on the claim wrong?
What would you check first? Keep reading, or jump to how the CO-96 denial was resolved.
What CO-96 means in plain English
Each part of the code answers a different question:
- CO (Contractual Obligation) means the provider carries the amount. CMS describes CO adjustments as amounts that are “generally… considered a write off for the provider and are not billed to the patient” (Medicare Claims Processing Manual, Ch. 22, §60.1).
- CARC 96 means the payer classed the charge as non-covered.
- The remark code (RARC) is the detail that says what kind of non-covered. It might be a benefit the law excludes, a code the payer doesn’t cover with that procedure, or a claim sent on the wrong form.
CO-96 is broader than CO-50. CO-50 is specifically a medical necessity decision. CO-96 covers anything the plan or the law doesn’t pay for, which is why the remark code matters so much here.
Denial code 96, CARC 96 and reason code 96: same thing?
Yes. Denial code 96, CARC 96 and reason code 96 all name the same X12 Claim Adjustment Reason Code. People drop the group code when they talk about it. On a remit, though, 96 always comes with a group code. The group code is what says who owes the money. So “CO-96” and “PR-96” share a reason but end with different people paying.
CO-96 vs PR-96 vs OA-96 vs PI-96
CARC 96 can come with any group code. The group code changes who owes the money:
| Group + 96 | Who carries the amount | Can you bill the patient? | When you’ll typically see it |
|---|---|---|---|
| CO-96 | Provider | No, unless your contract and the patient’s prior written agreement allow it | A billing or format problem (for example M117), or a non-covered line your contract makes you absorb |
| PR-96 | Patient | Yes, under your contract and any notice rules | A benefit the patient’s plan or the law excludes, such as a Medicare statutory exclusion (N425) |
| OA-96 | Neither group fits | Check the remark code and your contract first | Rare on 96. Used “when no other group code applies” (CMS Ch. 22, §60.1) |
| PI-96 | Payer-initiated reduction | No | Non-Medicare remits only. CMS lists just CO, OA and PR as valid on Medicare remittances |
The Medicare pattern in the remark code table below shows the split well. Noridian’s JE Part B top denials for Q4 2025 listed PR-96 with N425 (statutorily excluded), while its provider-liability pairings for 96 (N431, M117) appear as CO-96.
Common causes of CO-96 (and the remark code each one brings)
CARC 96 is a broad code. The cause is in the remark code. Use this table to match the cause to a fix. Remark code wording is checked against the X12 RARC list. Payers pick their own pairings, so treat the RARC column as a common match, not a fixed rule.
| Cause | Typical RARC | Fix |
|---|---|---|
| The law excludes the service from Medicare (cosmetic surgery, routine physicals) | N425 | Check the code first. If it is truly excluded, bill with GY, give a voluntary ABN and bill the patient under PR-96. |
| The code isn’t covered with the procedure billed with it | N431 | Check the code pair and modifiers. Correct it, or appeal with the coverage policy. |
| Paper claim from a provider who must bill Medicare electronically | M117 | Resubmit the same line electronically. Don’t bill the patient. |
| Plan benefit limit or exclusion (commercial plans) | N130 | Read the plan benefit documents and the 835 REF policy. Write off, or bill the patient only if your contract and their written consent allow it. |
| Diagnosis on the claim doesn’t support coverage | N569 | Check the ICD-10-CM code and its link to the line. Send a corrected claim if the diagnosis was wrong. |
| Local coverage rules (LCD) not met | N115 | Read the LCD criteria and the record. Appeal with records that meet the criteria. |
| National coverage rules (NCD) not met | N386 | Check the NCD in the Medicare Coverage Database. Appeal if the record meets it. |
| Item doesn’t fit the category it was billed under | N180 | Check the HCPCS code and category. Rebill under the right one. |
| Service isn’t part of the patient’s benefit package | N216 | Verify benefits for that service. Bill the right plan or follow your contract. |
| Not covered, with patient liability capped at the PR amounts | N174 | Bill the patient only the PR amounts on the remit. Write off the rest. |
| No prior authorization | Many payers use CARC 197 instead. N54 if the claim doesn’t match the auth | Get a retro auth if the payer allows it. See CO-197. |
| Coverage ended before the date of service | Usually CARC 27 instead | Recheck eligibility and bill the right payer. See CO-27. |
| Wrong payer or out of network | Usually CARC 109. N52 if the patient isn’t in your managed care plan | Find the right payer or plan and resend. See CO-109. |
| Benefit maximum reached | Usually CARC 119 instead | Check the plan limit. Bill the patient only if the plan and your contract allow it. |
| Another payer should pay first (COB) | Usually CARC 22 instead | Update coordination of benefits and bill the primary payer first. |
If your remit shows 96 for one of the last five causes, call the payer. Ask why it used 96 and not the more specific code. The answer often tells you the fastest fix.
Remark codes that come with CO-96
X12 requires at least one non-Alert remark code with 96. The first three rows are pairings Medicare contractors publish. The rest are X12 remark codes that describe a non-covered reason and often appear with 96.
| RARC | Official X12 text | What it points to | Published by |
|---|---|---|---|
| N425 | “Statutorily excluded service(s).” | The law excludes the service from Medicare. Usually reported as PR-96 | First Coast (#5 denial, Apr to Jun 2026), Novitas JL, Noridian JE (PR-96/N425) |
| N431 | “Not covered with this procedure.” | A code Medicare doesn’t cover in this situation, such as some ambulance or MolDX lines | Noridian JE Part B |
| M117 | “Not covered unless submitted via electronic claim.” | A paper CMS-1500 from a provider who must bill electronically | Noridian JE Part B |
| N130 | “Consult plan benefit documents/guidelines for information about restrictions for this service.” | A plan benefit limit or exclusion. Common on commercial remits | — |
| N115 | “This decision was based on a Local Coverage Determination (LCD). An LCD provides a guide to assist in determining whether a particular item or service is covered. A copy of this policy is available at www.cms.gov/mcd, or if you do not have web access, you may contact the contractor to request a copy of the LCD.” | The MAC’s local coverage rule wasn’t met | — |
| N386 | “This decision was based on a National Coverage Determination (NCD). An NCD provides a coverage determination as to whether a particular item or service is covered. Visit CMS.gov and search for Medicare Coverage Database to find a copy of the policy.” | A national Medicare coverage rule wasn’t met | — |
| N569 | “Not covered when performed for the reported diagnosis.” | The diagnosis doesn’t support coverage for this service | — |
| N180 | “This item or service does not meet the criteria for the category under which it was billed.” | Billed under the wrong category, common on DME lines | — |
| N216 | “We do not offer coverage for this type of service or the patient is not enrolled in this portion of our benefit package.” | The plan has no benefit for this service type | — |
| N174 | “This is not a covered service/procedure/ equipment/bed, however patient liability is limited to amounts shown in the adjustments under group ‘PR’.” | You may bill the patient only the PR amounts | — |
All RARC wording is quoted from the X12 RARC list, checked 20 October 2026. Rows with a dash in the last column are for reference. We didn’t find a Medicare contractor table that pairs them with 96.
Where CO-96 shows up in the 835
On an electronic remittance (835), the denial sits in the service line loop. Here’s a trimmed, illustrative example for a $185.00 line:
SVC*HC:99213*185.00*0.00**1~
DTM*472*20260915~
CAS*CO*96*185.00~
LQ*HE*N431~
REF*0K*POLICY-REF-0123~
CAS*CO*96*185.00is the group code, reason code and adjusted amount.LQ*HE*N431is the remark code. HE marks it as a remittance advice remark code.REF*0Kis the Healthcare Policy Identification segment that X12’s usage note tells you to check. When a payer sends it, it identifies the policy behind the denial.
On a paper EOB or a Medicare Standard Paper Remittance, look for “CO 96” in the adjustment column and the remark code in the remarks column or footnotes.
How to fix CO-96: decision path

- Read the group code and every remark code. CO-96 and PR-96 call for different actions, and the RARC tells you which branch you’re on.
- Check the claim for a fixable error first. Wrong CPT or HCPCS code, wrong diagnosis, a missing modifier, or the wrong claim format can all produce 96. First Coast’s advice for statutorily excluded denials starts the same way: “Review the service billed to ensure the correct code was submitted” (FCSO, PR 96 tips).
- If you find an error, correct and resubmit. For Medicare, resend only the corrected line so you don’t trigger an OA-18 duplicate. For M117, Noridian’s next step is simply “Resubmit claim electronically.” For other payers, follow the corrected claim process in the provider manual.
- If the claim was right and the service is a covered benefit, appeal. Noridian notes that items denied with CO-96/N431 “have appeal rights.” Attach the policy or benefit language that shows coverage, plus the records. Medicare redeterminations are due within 120 days of receiving the initial determination (CMS). See our Medicare appeals guide.
- If the service really isn’t covered, decide who owes it. PR-96: bill the patient under your contract and notice rules. CO-96: write the amount off unless your contract allows billing the member with their prior written consent.
- Fix the root cause. Add a front-end check for non-covered services and update scrubber edits so the same line doesn’t go out again.
Example scenario (fictional names), part 2
How the CO-96 Denial Was Resolved
- Diagnosis: Ken read CARC 96 as non-covered. The CO group put the amount on the practice, and N569 pointed at the diagnosis. The chart showed a nevus that had grown and bled, not a cosmetic request. A template had filled in Z41.1.
- Fix: the coder confirmed D22.5 (melanocytic nevi of trunk) from the note and pathology report. Ken sent a corrected claim with D22.5 linked to 11402.
- Outcome: the plan processed the corrected line as covered. The practice removed Z41.1 from the excision template.
Names and details are illustrative; no real patient data.
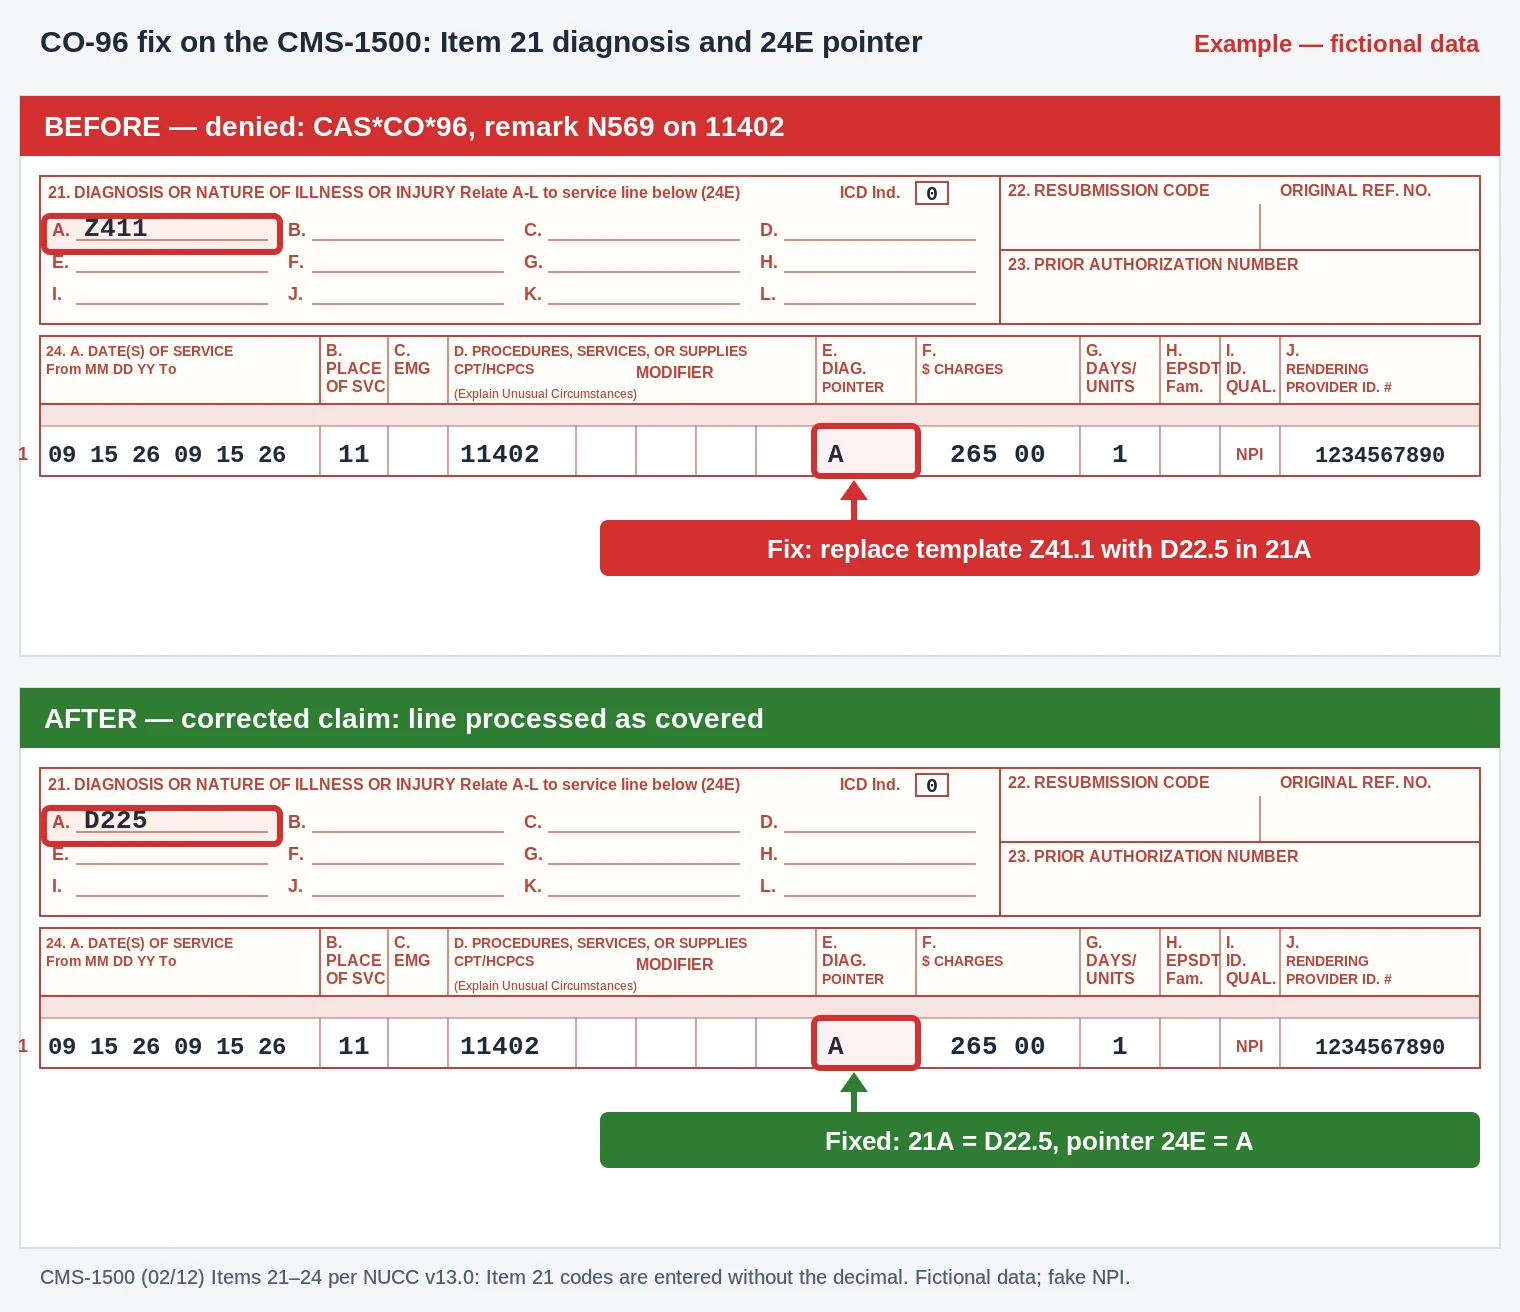
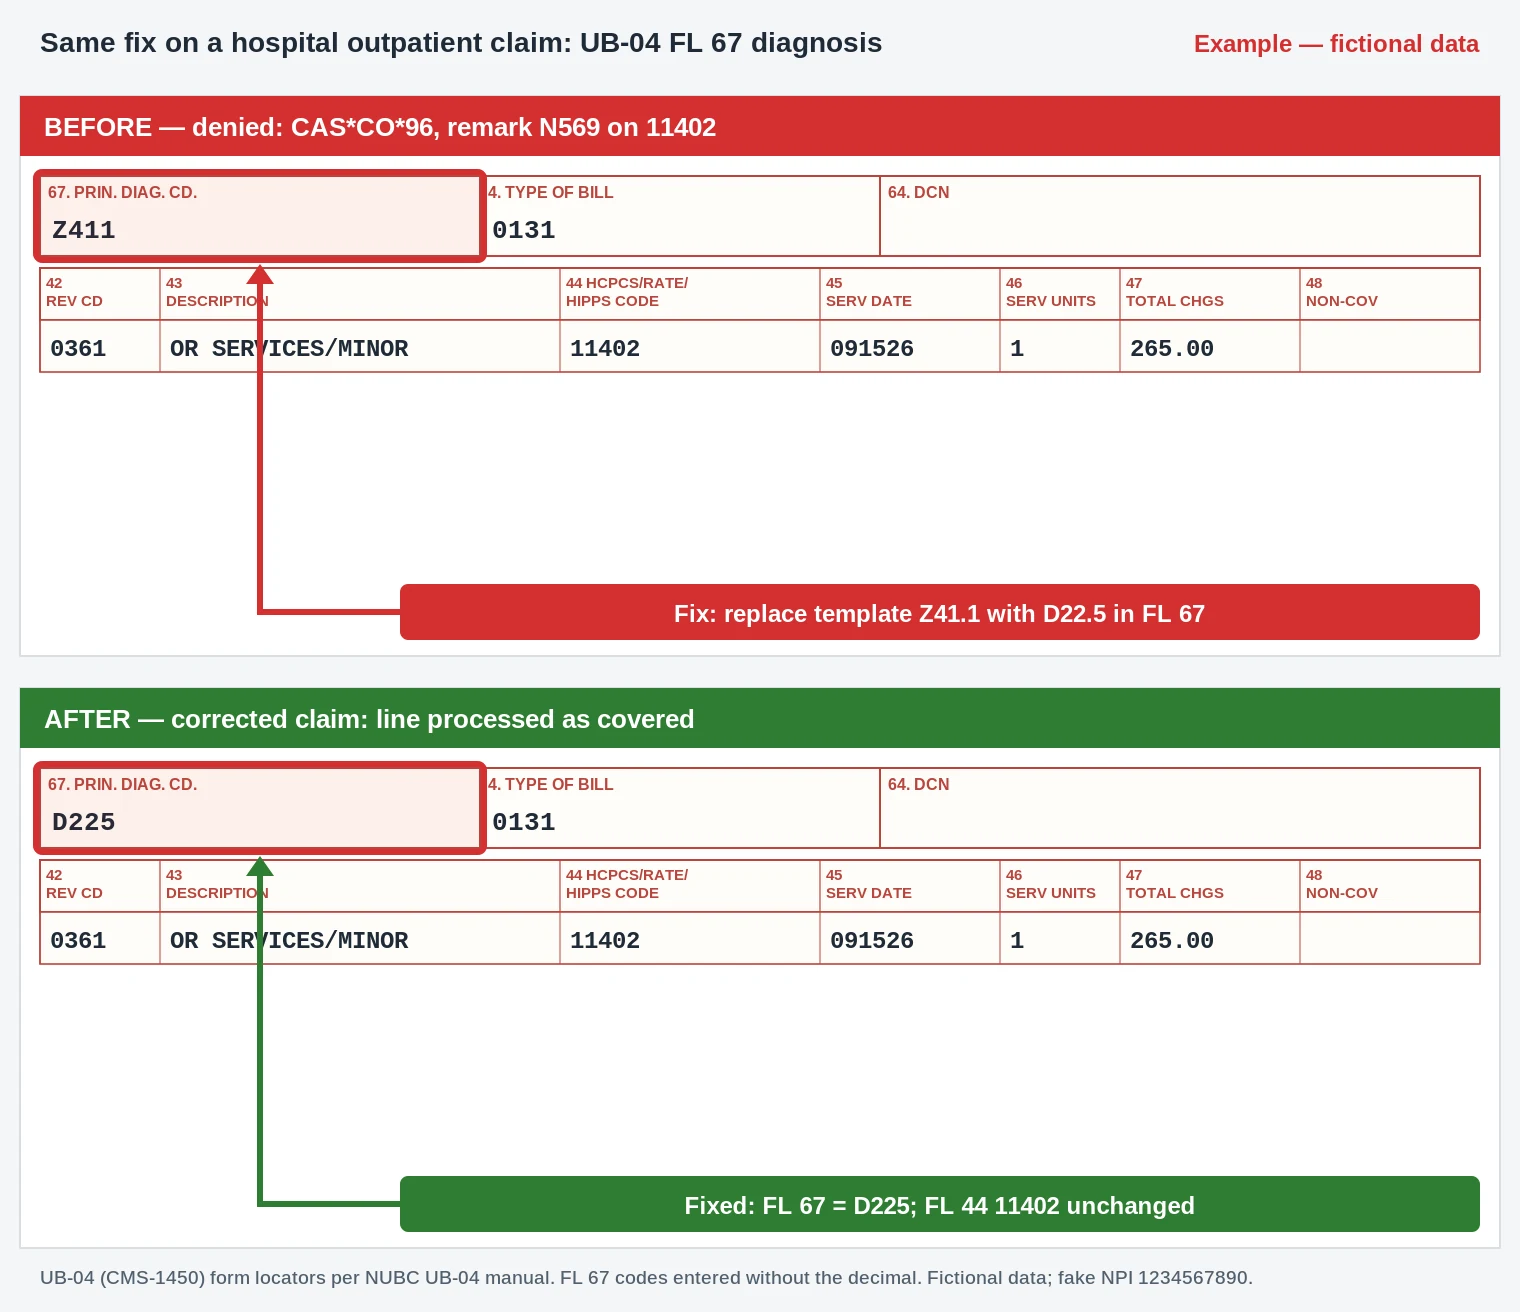
- Box 21A / FL 67: Z41.1 (encounter for cosmetic surgery, filled in by the template) replaced with D22.5 (melanocytic nevi of trunk), per the note and pathology report.
- Box 24E: pointer A links 11402 to D22.5. The UB-04 has no line pointer; FL 67 applies to the claim.
- Box 24D / FL 44: 11402 is unchanged. The procedure was right; the diagnosis was wrong.
Medicare and major payer notes
Original Medicare. Statutory exclusions are services Medicare never covers, such as cosmetic surgery, routine physicals, and hearing aids or hearing exams (CMS MLN906765, September 2025). First Coast says you “can append a GY modifier” to a line for statutorily excluded services. The modifier signals the item “does not meet the definition of a Medicare benefit.” An ABN isn’t required for care that’s never covered, but CMS “strongly encourage[s]” issuing one voluntarily (Medicare Claims Processing Manual, Ch. 30, §50.2.1). Our GY modifier guide covers the modifier in detail.
Medicare paper claims. M117 means Medicare expected an electronic claim. Noridian notes that if one provider in a group has the electronic filing requirement, “all members of group must submit electronically,” and providers who qualify can apply for an exemption under the Administrative Simplification Compliance Act.
UnitedHealthcare (commercial). Providers “may not seek or collect payment from a member for services not covered by the applicable benefit plan unless first obtaining the member’s written consent,” UHC’s medical policy bulletins say. That consent must acknowledge “that the service is not covered by the benefit plan and that they will be billed directly for the service” (UHC Medical Policy Update Bulletin, September 2026). Without that signed consent, treat a CO-96 from UHC as a write-off or an appeal, not a patient bill.
Other commercial and Medicaid plans. Rules on billing members for non-covered services sit in your participation agreement and, for Medicaid, in state rules. Read the remark code and the 835 REF policy reference, then check the plan’s benefit documents before you bill anyone.
Questions to ask the payer about a CO-96
Sometimes the remit alone won’t tell you enough. Before you call, have the claim number, date of service, member ID and billed codes ready. Then ask:
- Which plan rule or policy made this line non-covered? Ask for its name or number.
- Is the exclusion in the member’s plan, or in my provider contract?
- Would a different code, modifier or diagnosis change the decision?
- Can I send a corrected claim, or must I file a written appeal?
- What is the deadline, and where do I send it?
- May I bill the member if they signed a waiver before the visit?
Write down the rep’s name, the date and the call reference. Payers often ask for that reference when you appeal later. Log the notes in your practice management system, too, so whoever picks up the account next can see what was promised.
Worked example (illustrative)
A practice that is required to bill Medicare electronically sends a paper CMS-1500 for an office visit, CPT 99213, billed at $185.00. The remit comes back:
CAS*CO*96*185.00withLQ*HE*M117
Reading it: CO means the provider carries the $185.00. M117 says the service isn’t covered “unless submitted via electronic claim.” Nothing is wrong with the visit, the code or the diagnosis.
Fix: resubmit the same line electronically through the clearinghouse. Don’t bill the patient. The resubmission still has to meet Medicare’s 12-month filing limit from the date of service (42 CFR 424.44).
Contrast: if the same remit had shown CAS*PR*96 with N425 on a cosmetic procedure billed with GY, the patient would owe the amount, and a voluntary ABN or similar notice before the service would have set that expectation.
CO-96 appeal letter template
Use this when the claim was billed correctly and you believe the service is a covered benefit. Replace the bracketed text.
[Date]
[Payer name] Appeals / Redetermination Unit
[Address or portal reference]

Re: Request for reconsideration of CO-96 denial.
Patient: [Name]   Member ID: [ID]
Claim number: [ICN / claim #]   Date of service: [MM/DD/YYYY]
Service: [CPT/HCPCS + modifiers]   Billed amount: [$]
Remit codes: CO-96, [RARC]

We request reconsideration of the denial above. The service is a covered
benefit under [plan document / Medicare benefit category / policy name and
section], which states: "[quote the coverage language]".

The claim was coded correctly: [CPT/HCPCS] describes the service documented
in the enclosed record, and the diagnosis [ICD-10-CM] supports it.
[If applicable: The remark code [RARC] does not apply because ...]

Enclosed: remittance advice, claim copy, [office note / operative report],
[policy excerpt]. Please reprocess the line for payment.

[Name, credentials]  [Practice, NPI]  [Phone / email]
If the denial came from a coding error instead, don’t appeal. Send a corrected claim.
CO-96 prevention checklist
- Check benefits for the specific service at scheduling, not just active coverage.
- Flag services your MAC or payer lists as excluded, and route them to a patient financial conversation before the visit.
- Use GY on Medicare lines for statutorily excluded services, and give a voluntary ABN or similar notice.
- Get written consent before a non-covered service for plans that require it, such as UHC commercial.
- Confirm whether your practice must bill Medicare electronically, and block paper claims in your PM system if so.
- Add scrubber edits for code pairs your payers list as “not covered with this procedure.”
- Track CO-96 and PR-96 separately in your denial reports. They have different owners and different fixes.
Related denial codes
- CO-50: not deemed a medical necessity. The closest sibling to 96.
- PR-204: “This service/equipment/drug is not covered under the patient’s current benefit plan.” Some payers use 204 where others use 96.
- CO-197: prior authorization was missing. Use it when the problem is the auth, not the benefit.
- CO-27: coverage ended before the date of service.
- CO-109: the claim went to the wrong payer or contractor.
- CO-97: the service is bundled into another one already paid. Not a coverage decision.
- CO-16: claim lacks information. Fix and resubmit.
- PR-1, PR-2 and PR-3: the patient’s deductible, coinsurance and copay.
Cosmetic and aesthetic services get their own guide: see billing cosmetic procedures to Medicare with the GY modifier.
FAQ
What is the CO 96 denial code description?
X12 describes CARC 96 as “Non-covered charge(s).” Its usage notes require at least one remark code and point you to the 835 policy reference segment (loop 2110 REF). With the CO group code, the provider carries the amount.
What does denial code CO 96 mean in medical billing?
It means the payer won’t pay the line because it treats the charge as not covered, and the provider can’t bill the patient for it under the CO group code. The remark code explains whether it’s an exclusion, a code problem or a claim format problem.
How do I fix a CO 96 denial?
Read the remark code, then check the claim for errors in the code, diagnosis, modifier or claim format. Correct and resubmit if you find one. Appeal with the coverage language if the service is a covered benefit. Write it off if it truly isn’t covered and you have no signed patient agreement.
Can I bill the patient for CO-96?
Not usually. CO means a provider write-off. You can bill the patient when the remit shows PR-96, or when your payer contract allows it and the patient signed a written agreement before the service.
What is the difference between CO-96 and PR-96?
The reason is the same, non-covered charge. The group code differs: CO-96 puts the amount on the provider, PR-96 on the patient. Medicare statutory exclusions with remark code N425 commonly come as PR-96.
Can a CO-96 denial be appealed?
Yes, when the payer got coverage wrong. Noridian notes that CO-96 lines with remark code N431 “have appeal rights.” If the denial came from your own coding or format error, a corrected claim is faster than an appeal.
Is CO-96 the same as denial code 96?
Yes. Denial code 96, CARC 96 and reason code 96 are one X12 code: “Non-covered charge(s).” The CO in front means the provider carries the amount. PR-96 puts it on the patient.
Does missing prior authorization cause CO-96 or CO-197?
Most payers report a missing auth as CO-197. Some send CO-96 instead. If the remark code points to the auth, such as N54, work it like a CO-197: ask for a retro auth, then appeal or correct.
What should I do if a CO-96 line has no remark code?
X12 requires at least one remark code with CARC 96, so the line is incomplete. Check the 835 for LQ and REF segments. If both are missing, call the payer and ask for the remark code.
Sources
- X12, Claim Adjustment Reason Codes (CARC 96, 50, 97, 16, 22, 27, 109, 119, 197, 204). CARC 96 Start 01/01/1995, Last Modified 07/01/2017. Accessed 20 Oct 2026.
- X12, Remittance Advice Remark Codes (N425, N431, M117, N130, N115, N386, N569, N180, N216, N174, N54, N52). Accessed 20 Oct 2026.
- CMS, Medicare Claims Processing Manual (IOM 100-04), Ch. 22, §60.1 Group Codes.
- CMS, Medicare Claims Processing Manual (IOM 100-04), Ch. 30, §50.2.1 Optional ABN Uses.
- CMS MLN906765, Items & Services Not Covered Under Medicare (September 2025).
- CMS, First Level of Appeal: Redetermination by a Medicare Contractor.
- 42 CFR 424.44, Time limits for filing claims.
- Noridian JE Part B, Non-Covered Charge (CO-96/N431), last updated Apr 30, 2025.
- Noridian JE Part B, Electronic Claim Submission Requirement (CO-96/M117), last updated Apr 2, 2025.
- First Coast Service Options, Top claim errors, Apr to Jun 2026.
- First Coast Service Options, Tips to prevent CARC PR 96 (Feb 16, 2026).
- Novitas Solutions JL, Top claim denials, Apr to Jun 2026.
- UnitedHealthcare, Commercial Medical Policy Update Bulletin, September 2026.
Last updated: 20 October 2026 by Manikandan J, CPC, CRCR. This page is educational and doesn’t replace payer-specific instructions. Spot an error? Email info@medicalbilling101.com. Read our editorial policy.
{“@context”: “https://schema.org”, “@graph”: [{“@type”: “DefinedTerm”, “@id”: “https://medicalbilling101.com/denial-codes/co-96/#term”, “name”: “CO-96”, “termCode”: “96”, “alternateName”: [“CO 96”, “CO96”, “Denial code 96”, “CARC 96”, “Reason code 96”], “description”: “Non-covered charge(s). At least one Remark Code must be provided (may be comprised of either the NCPDP Reject Reason Code, or Remittance Advice Remark Code that is not an ALERT.)”, “url”: “https://medicalbilling101.com/denial-codes/co-96/”, “inDefinedTermSet”: “https://medicalbilling101.com/denial-codes/”, “subjectOf”: “https://x12.org/codes/claim-adjustment-reason-codes”}]}Related denial codes
- CO-114: Procedure or Product Not Approved by the FDA
- CO-56: Treatment Not Proven Effective
- CO-55: Experimental or Investigational Service
- CO-51: Pre-Existing Condition Not Covered
- PR-49: Routine or Preventive Exam Not Covered
- PR-157: Service Provided as a Result of an Act of War
- PR-158: Service Provided Outside the United States
- CO-159: Service Provided as a Result of Terrorism